How is defined the anion gap and why does albumin matter?
The anion gap is a calculated value from a standard electrolyte panel that assists clinicians in assessing acid-base disorder patterns, especially metabolic acidosis. It is derived from routine laboratory measurements, most often serum sodium, serum chloride, and serum bicarbonate. Because it is a computed number rather than a directly measured one, the anion gap is best thought of as a initial and diagnostic clue that needs clinical interpretation in context.
Albumin matters because it is a major unmeasured anion in blood. When albumin is low, the measured anion gap can look artificially normal or only mildly elevated even when there is serious metabolic acidosis underneath. This is a classic example of how an electrolyte imbalance can alter acid-base balance assessment. In other words, low albumin can underestimate the true severity of an acid-base problem.
This is where the anion gap calculator becomes useful, especially when it includes a correction for hypoalbuminemia. A corrected value gives a better assessment of the laboratory picture and can change the diagnosis, workup, and treatment plan. It is particularly important when there is concern for high anion gap metabolic acidosis, because a low albumin state can make the gap appear deceptively reassuring.
Common acid contributors such as lactate and ketones may be present even when the uncorrected anion gap seems normal. That is why the corrected value is often more useful in practice than the raw number alone.
What’s the adjusted anion gap formula for low albumin?
The most commonly used corrected anion gap formula adjusts the measured gap up when serum albumin concentration is below normal. The usual albumin correction factor employed in numerous clinical situations is:
Corrected anion gap = measured anion gap + 2.5 × (4.0 - serum albumin in g/dL)
This anion gap equation relies on a normal albumin of 4.0 g/dL. If albumin is reported in g/dL and is below normal, the correction adds to the gap by 2.5 mEq/L for every 1 g/dL decrease below 4.0 g/dL. The result is reported in mEq/L.
For example, if the measured anion gap is 10 mEq/L and the serum albumin is 2.0 g/dL, the correction is:
- 4.0 - 2.0 = 2.0 2.0 × 2.5 = 5.0 10 + 5 = 15 mEq/L corrected
That adjustment may move the patient from a seemingly normal reference range into a clearly elevated range, which is important for detecting an underlying acid load. This is why the anion gap calculator should be used with care when albumin is low.
There are slightly different described correction factors in the literature, but the 2.5 mEq/L per 1 g/dL albumin decrease remains the most common and convenient clinical formula for routine use in 2026. The goal is not perfect precision in every case; the goal is a better assessment of the true clinical interpretation.
How to work out the adjusted anion gap in steps
Working with an anion gap calculator is convenient, but knowing the manual calculation is important for safe interpretation. The usual first step is to derive the uncorrected anion gap from the measured sodium, chloride, and bicarbonate values.
Raw anion gap = serum sodium - (serum chloride + serum bicarbonate)
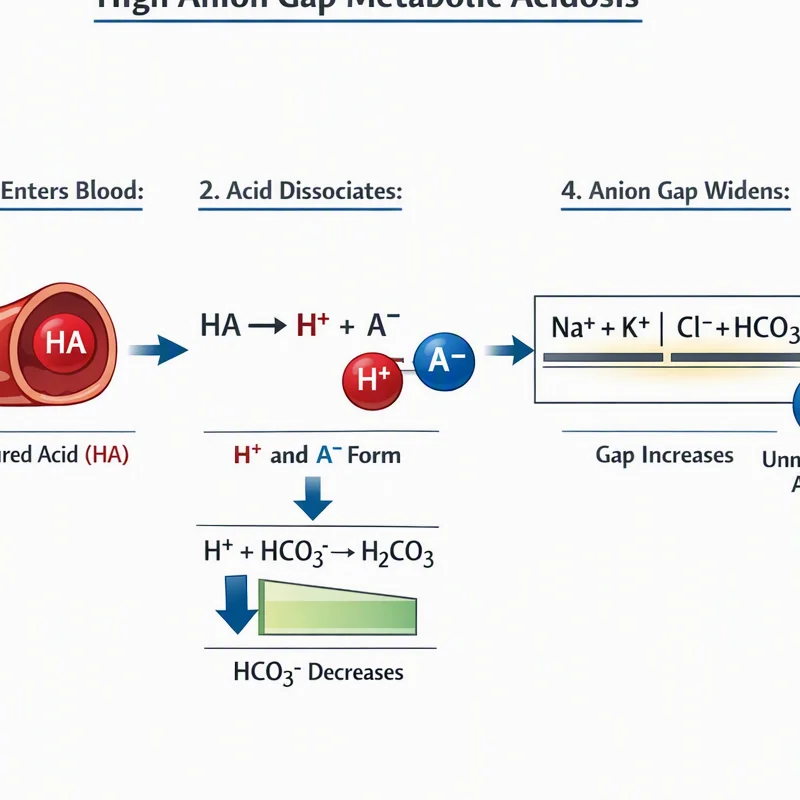
Step 1: Record the serum values from the electrolyte panel. For instance:
- Serum sodium: 140 mEq/L Serum chloride: 102 mEq/L Serum bicarbonate: 18 mEq/L Albumin: 2.4 g/dL
Step 2: Determine the measured anion gap.
140 - (102 + 18) = 140 - 120 = 20 mEq/L
Step 3: Use the albumin correction factor.
4.0 - 2.4 = 1.6
1.6 × 2.5 = 4.0
Step 4: Apply the correction to the measured gap.
20 + 4.0 = 24 mEq/L corrected anion gap
This corrected value suggests a clearer signal for high anion gap metabolic acidosis than the measured gap alone. In this example, the anion gap calculator helps prevent missing a clinically important disorder.
When you calculate the gap manually, be sure the units are aligned and that the values come from the same laboratory measurement time. The most useful results come from a clear clinical context, not from isolated numbers interpreted in a vacuum.
What albumin adjustment factor is used in 2026?
The practical 2026 formula still relies on the same correction used commonly in modern practice: apply 2.5 mEq/L to the anion gap for each 1 g/dL decline in normal albumin below 4.0 g/dL. Albumin is expressed in g/dL, and the corrected gap is expressed in mEq/L.
This correction is still widely used because it is easy, fast, and easy to integrate into bedside reasoning or an automated anion gap calculator. While some sources describe other constants, the 2.5 factor is still the most clinically recognizable and is often the default assumption in many clinical tools.
Why does this matter in 2026? Because the core issue has not changed: a low serum albumin concentration reduces the measured anion gap and can obscure the true acid-base picture. The correction improves accurate assessment of the patient’s acid burden and supports better diagnosis and evaluation.
It is also worth remembering that the correction is an inferential value, not a perfect physiological measurement. It should be used as a guide that improves interpretation, especially when other findings suggest a occult acidosis or another acid-base disorder.
When should a low albumin correction be considered?
Albumin correction for low levels should be considered any time the patient has marked hypoalbuminemia and the anion gap is being used to check for possible acid-base issues. This matters especially in critical illness, where albumin often decreases and the laboratory picture can lead to confusion.
It is often useful to correct in cases including:
- Evaluation of unexplained metabolic acidosis Potential high anion gap metabolic acidosis with a borderline measured gap Cases where the measured gap looks normal but lactate or ketones are elevated Patients with kidney disease who might have mixed acid-base issues Patients with liver disease and lower albumin production
In kidney disease, acid retention can raise the true anion gap while albumin remains low, creating a falsely modest uncorrected result. In liver disease, low albumin synthesis can make the measured gap seem lower than expected. In critical illness, fluid shifts, inflammation, nutrition problems, and organ dysfunction often interact to complicate interpretation.
Even so, not every patient with hypoalbuminemia requires formal correction in every situation. If the clinical question is not acid-base related, the correction may be less important. But if the purpose is to evaluate acidosis, the adjusted value is usually much more informative.
How should you read a corrected vs uncorrected anion gap?
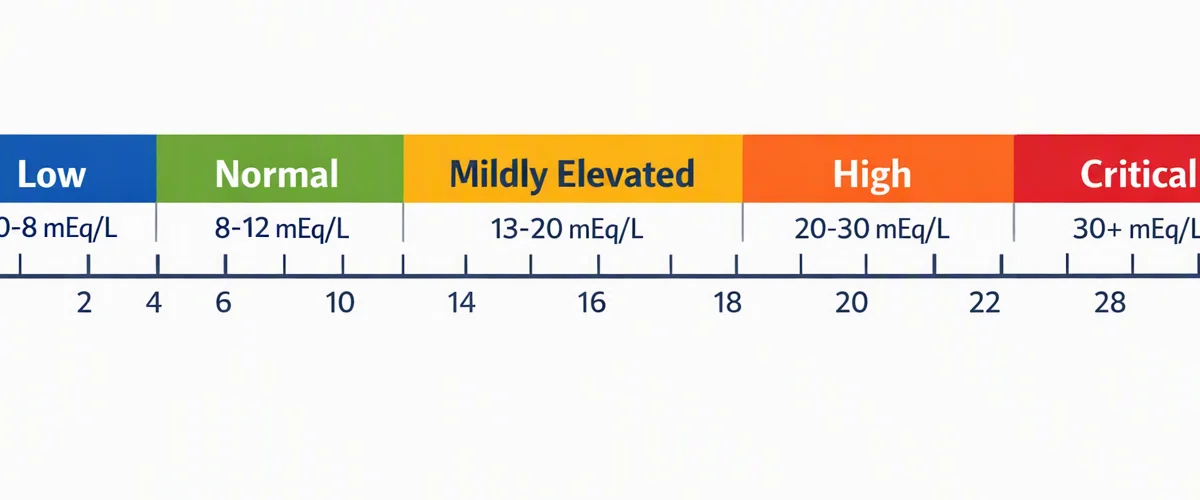
The contrast between corrected and uncorrected results can dramatically alter clinical interpretation. A normal measured value does not always exclude a real high anion gap process if albumin is low. Conversely, a mildly elevated measured gap may appear more definitively abnormal after correction, supporting the case for organic acids such as lactate or ketones.
A gap that appears normal may still coexist with an acid burden if albumin is reduced. After correction, the result may move into a clearly elevated range, uncovering a hidden acidosis interpretation that would otherwise be missed. This is one reason clinicians use the corrected value to guide the diagnostic workup.
Example interpretation:
- Uncorrected normal anion gap: can still indicate true high-gap acidosis if albumin is low Corrected elevated anion gap: indicates a high-gap process and should prompt evaluation for lactate, ketones, toxins, or renal causes Corrected normal anion gap: suggests that the measured elevation may have been explained mainly by low albumin or that no major high-gap process is present
The relationship with base excess can also be useful. Base excess reflects metabolic component severity, while the corrected anion gap helps determine whether unmeasured anions are present. When combined, they can improve acid-base balance assessment and reduce missed diagnoses.
In summary, the corrected result is often more clinically meaningful than the raw laboratory value, especially when evaluating suspected acid-base disturbance in the setting of low albumin.
Typical sources of decreased albumin and acid base disorders
Low albumin is not a diagnosis by itself; it is a clue. Various conditions can reduce albumin and impact acid-base balance at the same time. Finding the cause helps guide the workup and support management.
Malnutrition can reduce albumin production and coexist with electrolyte imbalance, poor intake, or catabolic stress. In such cases, the measured anion gap may be lower than expected, masking metabolic changes.
Nephrotic syndrome causes urinary protein loss and can lead to marked hypoalbuminemia. This can distort the measured anion gap while also being associated with kidney-related acid-base problems.
Cirrhosis and other forms of liver disease decrease albumin synthesis and often occur with fluid shifts, inflammation, and altered clearance of organic acids. The result may be a complex laboratory picture unless the corrected anion gap is considered.
Inflammation and critical illness can reduce albumin through reduced synthesis, redistribution, and increased catabolism. These states also increase the risk of lactic acidosis, sepsis-related metabolic changes, and other complex acid-base disorders.
All of these causes support the same message: low albumin can alter the interpretation of the electrolyte panel, so a corrected approach improves diagnostic accuracy. When the clinical picture suggests acidosis, the corrected anion gap should be part of the assessment.
FAQs about the corrected anion gap formula
What is the corrected anion gap formula for low albumin?
The commonly used formula is: corrected anion gap = measured anion gap + 2.5 × (4.0 - serum albumin in g/dL). It is a practical clinical formula that adjusts for the effect of low albumin on the measured laboratory value.
Why does low albumin lower the measured anion gap?
Albumin is a major unmeasured anion in blood. When albumin falls, the measured anion gap falls too, even if other acids are present. This can cause the lab result to underestimate the severity of an acid-base problem.
Which albumin level is supposed to be used for correction?
Use the patient’s current serum albumin level based on the same laboratory assessment, preferably reported in g/dL. The correction is typically calculated on a typical albumin reference of 4.0 g/dL.
Does all patients with hypoalbuminemia need to have an anion gap correction?
Not necessarily. The correction is most useful when evaluating acid-base status, especially if metabolic acidosis is thought to be present. If the anion gap serves for a another purpose, the correction might not be needed, but it is often helpful in clinical assessment of acidosis.
How do you read a normal corrected anion gap in acidosis?
If the corrected gap is normal, it implies that unmeasured anions are not driving the disorder and that the patient may have a normal anion gap metabolic acidosis or another non-gap process. In that https://penzu.com/p/2c224bd150ea0273 situation, assess the full acid-base picture, including bicarbonate, chloride, base excess, and the broader clinical context.