What the Anion Gap Shows in Renal Disease
The anion gap is a useful way to approximate how much undetected acid is found in the circulation. In renal disease, that matters because impaired kidney function can affect electrolytes and contribute to metabolic acidosis. The result is not a diagnosis by itself, but it is a valuable interpretation tool for understanding whether acid accumulation, electrolyte imbalance, or another metabolic disturbance may be present.
In standard clinical assessment, the anion gap helps identify whether the body is dealing with excess acids that are not directly measured on a standard serum chemistry panel. Kidney-related problems can change this number upward or sometimes leave it within a normal reference range even when acidosis is present. That is why interpretation in the setting of kidney disease requires more than a single laboratory result.
When kidney function declines, the body may have trouble removing acids and preserving acid-base balance. Over time, this can produce a detectable change in serum values, especially sodium, chloride, and bicarbonate. The anion gap is a simple calculation, but its clinical meaning depends on the broader context, including kidney function, albumin level, and the likely etiology of the abnormality.
How to Work With an Anion Gap Calculator
An Anion Gap Calculator uses key laboratory inputs from a serum chemistry panel, usually sodium, chloride, and bicarbonate. Some tools also include albumin adjustment, which is especially important in kidney disease because low albumin is common and can mask the severity of the acid-base disorder.
To use the calculator correctly, enter the most recent laboratory values exactly as reported. The result is only as accurate as the inputs, so confirm the units and the collection time. In practice, the calculator supports calculation and initial interpretation, but it does not replace clinical judgment, diagnostic evaluation, or follow-up testing when needed.
A common process is:
- Review the serum chemistry panel for sodium, chloride, and bicarbonate. Place the values into the Anion Gap Calculator. Determine if albumin is low and apply a correction factor if needed. Assess the result with the usual reference range and the patient’s kidney function. Apply the result as part of screening and risk stratification for metabolic acidosis.
Because renal disease often changes multiple parameters at once, the calculator is best used as part of a broader clinical assessment. A mildly abnormal result may indicate compensation, volume status, or mixed disorders rather than a single cause.
Anion Gap Formula and Calculation Basics
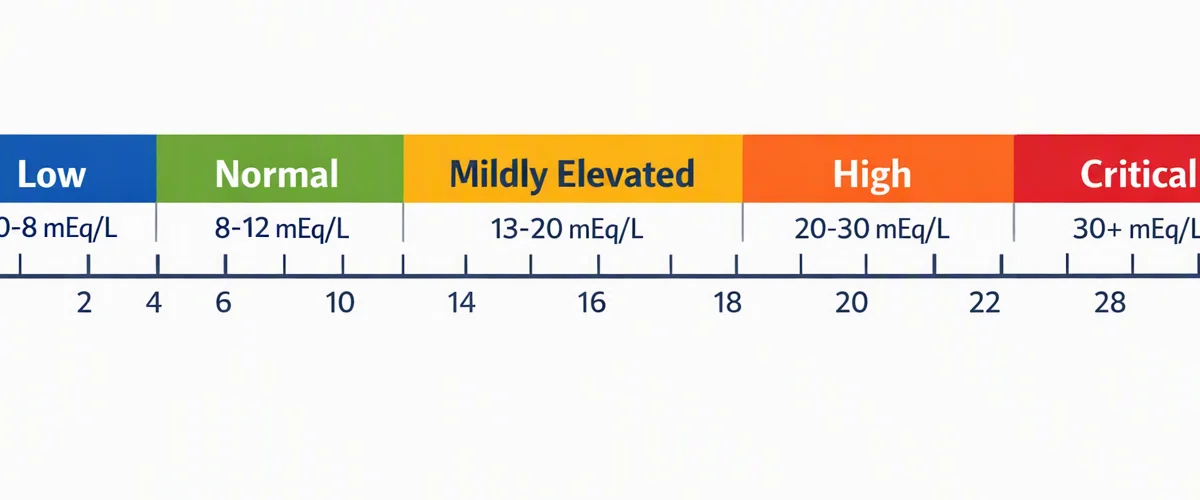
The usual anion gap formula is frequently expressed as sodium minus chloride minus bicarbonate. Certain laboratories include potassium, but standard interpretation relies on the more basic version. The concept is straightforward: the calculation approximates the gap between measured cations and measured anions, which indirectly reflects unmeasured ions and acids in the blood.
A normal anion gap means the calculation falls within the expected laboratory reference range. A high anion gap indicates accumulation of unmeasured acids, which can occur in renal failure, lactic acidosis, ketoacidosis, or toxin exposure. In kidney disease, the key point is not just whether the value is elevated, but whether the pattern aligns with the overall clinical picture.
Interpreting the result also depends on laboratory values and local standards. Different labs may report marginally different reference ranges because of analytic methods and albumin effects. For that reason, it is best to review each laboratory result in context rather than relying on a single cutoff.
Practical point: a “normal” result does not always mean there is no acid-base problem. In renal disease, albumin, bicarbonate, and other serum values may alter the calculation enough to obscure the underlying abnormality.
Why Kidney Failure Can Raise the Anion Gap
In chronic kidney disease, the kidneys slowly lose the ability to eliminate acids and regenerate bicarbonate, which can result in acid retention. As the condition advances, this may produce a increased anion gap, especially when unmeasured acids gather faster than they can be excreted. The degree of elevation often shows severity and the balance between ongoing acid load and kidney function.
Acute kidney injury can also elevate the anion gap. When renal clearance falls suddenly, retained acids may collect quickly, and the patient can develop renal failure-related metabolic disturbance. In these settings, the elevated value may suggest a need for immediate clinical evaluation, especially if there are symptoms, worsening kidney function, or other abnormal laboratory findings.
Uremia is a classic renal cause of increased anion gap. It represents the buildup of nitrogenous waste products and other unmeasured acids that the kidneys normally remove. As uremia intensifies, acid-base balance becomes harder to maintain, and the calculator result may help reveal the extent of the metabolic burden.
In practice, an elevated anion gap in kidney disease often suggests a combination of mechanisms rather than a single abnormality. The result should be considered alongside the patient’s history, medications, volume status, and trend in kidney function.
Correcting the Anion Gap for Low Albumin
Albumin is a major unmeasured anion in the blood, so when albumin is low, the computed anion gap may appear falsely normal or only mildly elevated. This is especially important in renal disease, where hypoalbuminemia can occur due to inflammatory processes, protein loss, malnutrition, or chronic illness. A low albumin level can hide clinically meaningful acidosis unless a corrected anion gap is used.
Albumin adjustment refines acid-base interpretation by accounting for the missing negative charge that albumin normally provides. In practical terms, the correction factor estimates what the gap would look like if albumin were within the usual range. This can change diagnostic thinking, particularly when the measured result seems indeterminate but the patient has signs of metabolic acidosis.
Using a corrected value is especially helpful when the clinical picture suggests kidney-related acid retention but the raw result is not striking. It also aids more accurate management decisions, since underestimating the severity of acidosis can delay treatment or further workup.
For best results, interpret the corrected anion gap with the rest of the acid-base data. Albumin correction betters analysis, but it should not be used in isolation. The most reliable approach combines the calculator, serum chemistry panel, and clinical assessment.
Reading Expected vs Increased Anion Gap in Renal Disease
Typical anion gap metabolic acidosis in renal disease often points toward bicarbonate loss or impaired acid secretion rather than accumulation of unmeasured acids. One major cause is kidney tubular dysfunction, where the kidneys cannot properly acidify urine or reclaim bicarbonate. This is often seen in forms of tubular injury and can be related to renal tubular acidosis.
Elevated anion gap metabolic acidosis usually indicates retained acids, including those related to uremia or other systemic processes. In kidney disease, this often becomes more prominent as filtration falls and acid handling worsens. However, an elevated value does not automatically prove kidney disease is the only cause, because concurrent disorders such as lactic acidosis may also contribute.
A normal result does not exclude renal involvement. Certain patients with kidney disease have a normal gap because they are losing bicarbonate in a tubular pattern or because the elevated acid load is balanced by low albumin. For that reason interpretation must distinguish between the type of acidosis and the stage of disease.
Clinicians often use the anion gap to narrow the differential diagnosis and decide what to evaluate next. The pattern helps with diagnosis, but it is most useful when integrated into the full acid-base picture.
Common Causes of Anion Gap Changes in Renal Patients
Various disorders can affect the anion gap in patients with kidney disease. Some stem directly from renal causes, while others are frequent metabolic complications that occur alongside renal dysfunction. The most important causes include renal tubular acidosis, uremia, lactate accumulation, and ketones.
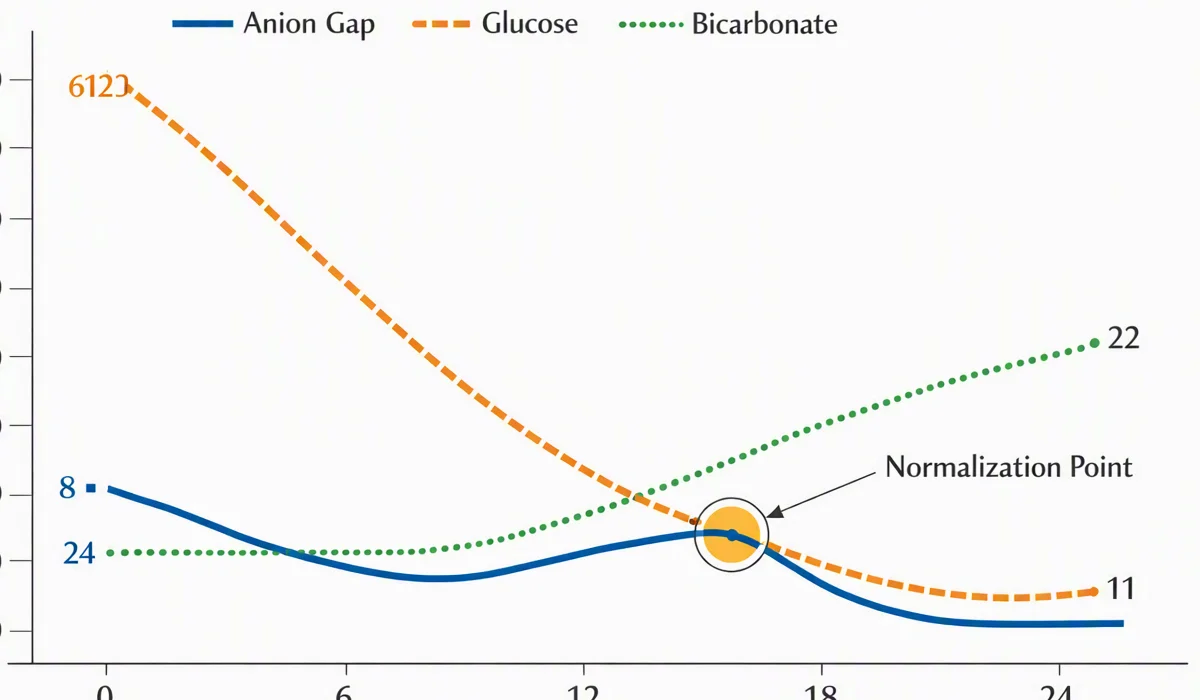
Renal tubular acidosis often produces a normal anion gap metabolic acidosis because the issue is impaired acid secretion or bicarbonate handling rather than buildup of unmeasured acids. By contrast, uremia in more advanced renal disease more often elevates the anion gap because retained organic acids build up in the bloodstream.
Lactate can increase in patients with poor perfusion, sepsis, hypoxia, or severe illness. If kidney function is impaired at the same time, clearance may be reduced and the acid-base disorder can become more pronounced. Ketones are another important cause, especially when there is poor intake, insulin deficiency, or catabolic stress.
- Renal tubular acidosis: commonly associated with normal anion gap metabolic acidosis. Uremia: commonly associated with high anion gap metabolic acidosis in advanced renal dysfunction. Lactate: may reflect tissue hypoperfusion or another systemic stressor. Ketones: may indicate fasting, diabetic ketoacidosis, or other catabolic states.
Since these causes can overlap, the calculator is best used as a initial guide for etiologic assessment rather than a final answer.
Clinical Setting: When a Calculator Alone Is Insufficient
The Anion Gap Calculator is helpful, but it cannot fully define an acid-base disorder. When the result is unexpected, the next step often includes an arterial blood gas and assessment of serum bicarbonate to establish the existence and extent of acidosis. This additional testing helps determine whether the body is compensating as expected or whether a mixed disorder is present.
The delta gap is another useful concept when interpreting a high anion gap. It contrasts the increase in the gap with the drop in bicarbonate and can suggest whether more than one metabolic disturbance is occurring. This is especially useful in renal disease, where the picture may include both retained acids and bicarbonate loss.
Clinical context matters because kidney disease rarely exists in isolation. The patient’s symptoms, medication list, hemodynamic status, infection risk, and recent trends in kidney function all affect interpretation. A calculator can identify an abnormality, but the diagnosis and management plan require a broader review.
Use the calculator as part of a stepwise process: evaluate, verify, correct, and contextualize. That approach supports safer decisions and better risk stratification when evaluating acid-base balance in renal patients.
Frequently Asked Questions
What is the anion gap and why does it matter in renal disease?
The anion gap is a calculation that estimates unmeasured acids in the blood. It matters in renal disease because impaired kidney function can lead to metabolic acidosis, acid retention, and electrolyte imbalance. The result helps identify whether the pattern is more consistent with high anion gap metabolic acidosis, normal anion gap metabolic acidosis, or another acid-base problem.
How do I use an Anion Gap Calculator correctly?
Enter the sodium, chloride, and bicarbonate values from the serum chemistry panel exactly as reported. If albumin is low, consider using a corrected anion gap because hypoalbuminemia can hide the abnormality. Then interpret the result together with kidney function, clinical assessment, and any supporting laboratory values such as an arterial blood gas.
What causes low albumin change the anion gap?
Albumin is a important unmeasured anion, so low albumin decreases the measured gap and can make the value appear deceptively normal. This is why albumin adjustment is crucial in kidney disease. A corrected anion gap offers a better estimate of the true acid-base status when hypoalbuminemia is present.
Can kidney disease cause a normal anion gap metabolic acidosis?
Yes. Kidney disease can cause normal anion gap metabolic acidosis, especially when kidney tubular dysfunction or renal tubular acidosis is present. In those cases, the problem is often bicarbonate loss or impaired acid secretion rather than accumulation of unmeasured acids. The pattern may differ from the elevated gap seen with uremia.
At what point should an elevated anion gap in kidney disease be evaluated further?
An elevated gap should be evaluated further when it is persistent, worsening, or accompanied by symptoms, low serum bicarbonate, or abnormal arterial blood gas https://anion-gap-calculation.com/formula/delta-ratio.html results. It also deserves follow-up when the cause is unclear or when other processes such as lactic acidosis or ketones may be contributing. In renal disease, the finding should always be interpreted in context rather than in isolation.