What exactly is an Anion Gap?
The anion gap is a derived figure used to assess an electrolyte panel and identify abnormalities in acid-base balance. It evaluates the primary measured serum electrolytes to determine whether there are extra unmeasured acids or other charged particles in the blood. In practical terms, an anion gap calculator gives a fast snapshot of whether the chemistry pattern points to a underlying metabolic issue.
Because the bloodstream must remain electrically balanced, the measured cations and anions do not perfectly correspond. The discrepancy is the anion gap. This makes it a helpful diagnostic clue in evaluating an acid-base disorder, especially when metabolic acidosis is suspected. Clinicians often use the result as a screening tool before deciding whether more testing https://anion-gap-help238.fotosdefrases.com/anion-gap-calculator-for-evaluating-electrolyte-disturbances is needed.
The concept is most relevant when paired with the rest of the serum chemistry picture. Sodium, chloride, and bicarbonate are the key measured values, but the result can also indicate the presence of unmeasured anions such as organic acids or albumin-related charges. That is why the anion gap is not just a number; it is part of a larger clinical interpretation process.
How the Anion Gap Calculator Operates
An anion gap calculator uses a basic formula based on sodium, chloride, and bicarbonate. The standard anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
This calculation estimates the difference between the main measured positive and negatively charged ions in the blood. Sodium is the most abundant measured cation in typical lab testing, while chloride and bicarbonate are the main measured anions. The connection among these values helps reveal whether the body has accumulated acids that are not directly measured on a routine panel.
The calculator does not confirm a disease by itself. Instead, it offers interpretation that can narrow the differential diagnosis. For example, a higher-than-expected result suggests increased acid burden, while a low result may point toward reduced protein charge, measurement issues, or unusual electrolyte patterns. The strength of the tool is its clinical utility: it rapidly connects the numbers to likely physiology.
Some versions of the calculation include potassium, but many common clinical approaches use sodium, chloride, and bicarbonate alone. For most users reviewing an electrolyte panel, the streamlined equation is the most familiar and most convenient to apply.
How to Determine Anion Gap Using a Basic Metabolic Panel
A basic metabolic panel usually includes the values needed for the computation: serum sodium, serum chloride, and serum bicarbonate. After those numbers are available, the formula is simple and can be done directly or with an online tool.
To work out the anion gap from a basic metabolic panel, use these steps:
- Identify the serum sodium value. Find the serum chloride value. Identify the serum bicarbonate value. Combine chloride and bicarbonate together. Deduct that sum from sodium.
The result is the anion gap. Because the panel is standardized serum chemistry, this is a quick way to obtain a calculation that supports evaluation of a possible metabolic disturbance.
For instance, if sodium is 140, chloride is 104, and bicarbonate is 24, then 104 + 24 = 128, and 140 - 128 = 12. That value may sit within the expected reference range depending on the laboratory method used. The important point is not only the number itself, but how it fits with the rest of the lab values and the patient’s condition.
Typical Anion Gap Range & Reference Intervals
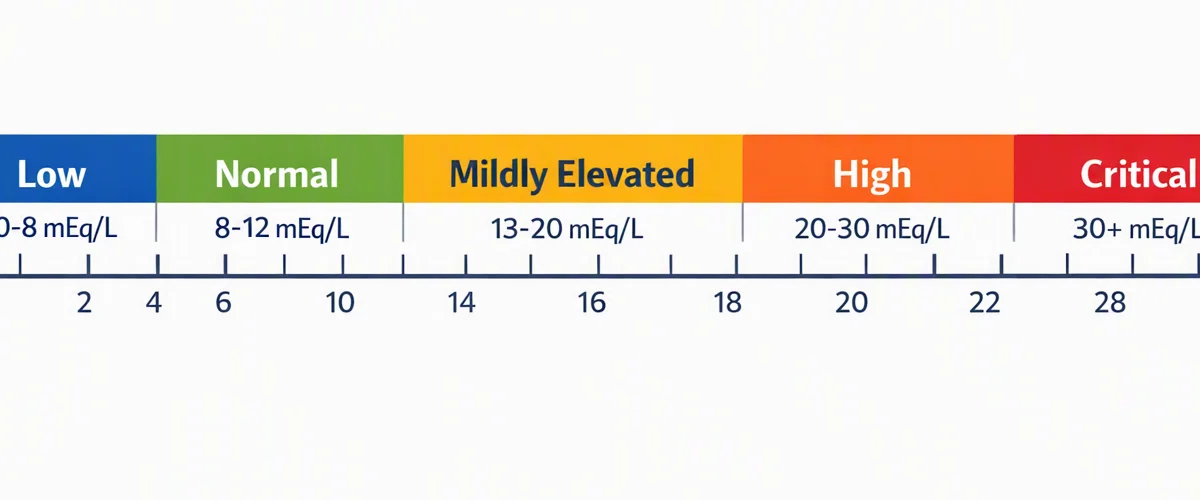
The typical range for anion gap depends on the laboratory and its specific testing method. Several analyzers and reporting systems can produce somewhat different reference interval values. That means the same result may be considered normal in one lab and equivocal in another.
One major factor is albumin, a negatively charged plasma protein that influences the apparent gap. Because albumin carries much of the unmeasured negative charge in blood, lower albumin can decrease the measured anion gap. This is one reason the result should always be read in context rather than treated as a standalone diagnosis.
Laboratory variation matters as well. The technique used for electrolyte measurement can affect the reported value, so the individual reference interval should be used whenever possible. In practice, clinicians focus on whether the number is clearly high, reduced, or unexpectedly normal given the acid-base picture.
In some settings, a slightly higher or lower result may still be acceptable if the overall clinical picture does not suggest a significant disorder. That is why the anion gap is best viewed as part of broader clinical interpretation rather than as an isolated cutoff.
High Anion Gap vs Normal Anion Gap Acidosis
Acidosis related to metabolism stands as a leading one of the main reasons to check an anion gap. A increased anion gap usually indicates that more acids are circulating in the blood, raising the number of unmeasured anions. A typical anion gap acidosis, by contrast, suggests that bicarbonate has been lost and replaced by chloride, so the overall gap stays about the same.
In a elevated anion gap state, acid is added to the body at a greater rate than it can be removed or buffered. In a typical anion gap pattern, the main problem is often a move in chloride and bicarbonate rather than an increase of new acids. That distinction supports shape the diagnostic differential and guide the next steps in evaluation.
Understanding the relationship between the gap and acid base balance also helps explain why the result matters. The body uses buffer systems to maintain stable pH. When those systems are overwhelmed, the chemistry panel may show a widened gap or a normal gap pattern that still reflects significant disease.
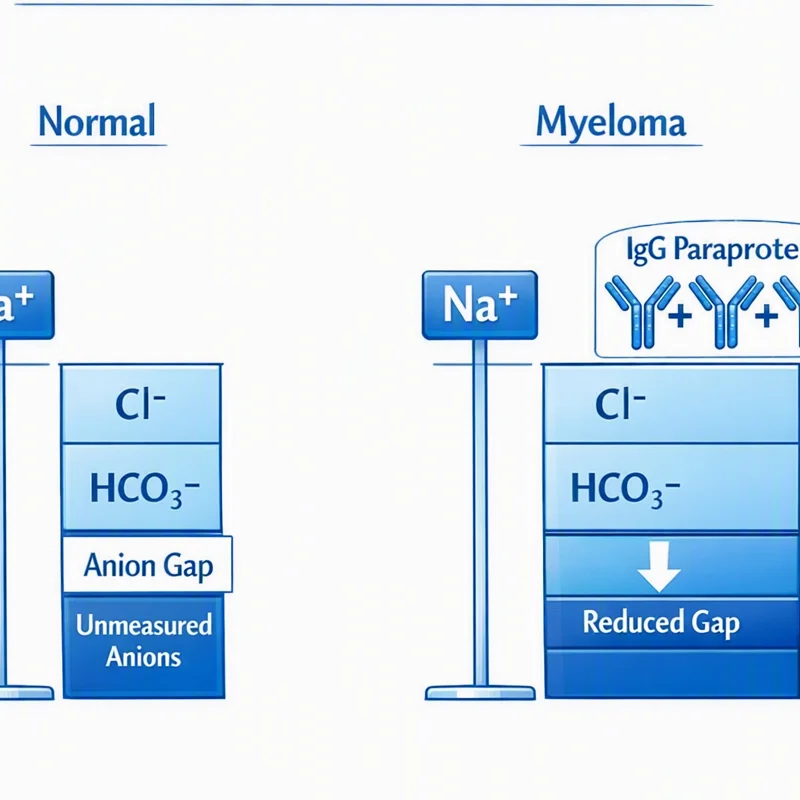
A reduced anion gap is rarer but can occur when albumin is reduced, when unmeasured cations are present, or when there is measurement artifact. It should not be ignored if it is unexpected, because it may be a clue to a separate issue affecting the serum chemistry pattern.
Typical Causes of an Elevated Anion Gap
An elevated result often suggests the build-up of acid compounds or other charged substances that are not directly measured in the panel. The most common causes include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion.
Lactic acidosis happens when lactate builds up, often because tissues are not receiving enough oxygen or because metabolism is otherwise stressed. This generates extra acid and raises the anion gap. Ketoacidosis, including diabetic ketoacidosis and other ketosis states, can also increase organic acids in the blood and widen the gap.
Renal failure can lead to acid retention because the kidneys are no longer clearing acids effectively. As acid accumulates, the anion gap rises. Toxin ingestion is another important category because certain ingested substances create acids or interfere with metabolism, producing a significant gap elevation.
Other causes can also exist, but these major categories are central to interpretation. An elevated result is not a final diagnosis; it is a signal to review symptoms, history, and additional labs. That is why the anion gap is best used as a diagnostic clue rather than a standalone answer.
How Reduced Albumin Alters the Anion Gap
Albumin powerfully affects the anion gap because it provides negative charge to the plasma. If albumin is low, the measured gap can seem lower than expected even though the underlying acid-base status is abnormal. That is why hypoalbuminemia can hide a clinically important problem.
A adjusted anion gap compensates for low albumin to more reliably reflect the true acid-base state. The need for correction arises from albumin’s role in protein electrical charge and the balance of charged particles in plasma. If this is not adjusted, a patient with significant metabolic disturbance may seem to have a less impressive result than they actually do.
The exact correction method can differ, but the overall idea is the same: lower albumin means the uncorrected number may underestimate the true gap. A corrected value can therefore strengthen clinical interpretation, especially when symptoms or other lab findings suggest acidosis.
Because albumin is so significant, any abnormal result should be reviewed alongside the protein level if available. This is particularly crucial when the anion gap appears normal despite signs of metabolic acidosis.
Step-by-Step Illustration With an electrolyte panel
This is an illustrative calculation based on typical electrolyte measurements taken from an electrolyte panel:
- Sodium: 138 Serum chloride: 100 Bicarbonate: 16
First: Add the chloride and the bicarbonate. 100 + 16 = 116.
Next: Take away that total from the sodium value. 138 - 116 = 22.
The result is an anion gap of 22.
This result is elevated in many reference systems and suggests a likely high anion gap pattern. The next question is not simply whether the number is high, but what the clinical context shows. If the patient has diabetes, poor intake, or vomiting, ketoacidosis may be a concern. If there is shock, infection, or low oxygen delivery, lactic acidosis becomes more likely. If kidney function is poor, renal failure may explain the finding.
Now, consider the same individual with an albumin of 2.5. In this situation, the uncorrected value might underestimate the degree of abnormality. A albumin-corrected anion gap can provide a more accurate interpretation and better capture the true metabolic disturbance. This is the reason the calculator is most useful when paired with the full lab picture rather than relied on in isolation.
Limitations of the Anion Gap Calculator
Like any screening tool, an anion gap calculator has limits. One key problem is measurement error. Small differences in how sodium, chloride, and bicarbonate are measured can change the final number, especially when the result is near the edge of the reference range.
Lab methods equally play a role. Distinct analysis technologies and electrolyte testing methods can yield different results, which is why the lab’s reference range should always be used. A value that appears out of range in one environment may be normal in another.
One more challenge is the role of unmeasured cations. Substances such as lithium or other positively charged ions can alter the calculation and reduce the apparent gap. Moreover, abnormal protein levels, changes in plasma proteins, and unusual clinical situations can create patterns that do not fit a simple formula.
Finally, the calculator cannot replace clinical interpretation. Signs, vital signs, blood gas results, kidney function, and glucose or lactate levels may be needed to understand what the result really means. The calculation is helpful, but it is only one piece of the assessment.
When to Seek Urgent Medical Evaluation
Certain anion gap abnormalities suggest a potentially dangerous illness that requires prompt attention. If there are signs of severe acidosis, the situation may become urgent quickly. Symptoms can include rapid breathing, confusion, marked weakness, severe nausea, vomiting, abdominal pain, or decreased responsiveness.
Very abnormal results or other critical values on the chemistry panel may signal a serious metabolic problem. When the gap is high and the patient is ill, immediate evaluation may be necessary to determine whether there is lactic acidosis, ketoacidosis, toxin exposure, or kidney failure.
Because the anion gap is a diagnostic clue, not a diagnosis, symptoms and the overall picture should guide the response. If there is concern for severe illness, emergency care is appropriate. Delay can be dangerous when the body is struggling to maintain acid-base balance.
Frequently Asked Questions
What is the anion gap on an electrolyte panel?
The anion gap is a calculated value from an electrolyte panel that helps assess acid-base balance. It estimates the difference between measured cations and measured anions, mainly using sodium, chloride, and bicarbonate. It is often used as a screening tool for metabolic problems.
How can you calculate anion gap using sodium, chloride, and bicarbonate?
Apply the formula for anion gap: sodium less the total of chloride and bicarbonate. In other words, Anion gap = serum sodium - (serum chloride + serum bicarbonate). This is the common computation used in an anion gap calculator.
What does a high anion gap mean?
A increased anion gap usually means that unmeasured acids are present, which is a frequent pattern in metabolic acidosis. Common causes include lactate accumulation, ketone buildup, renal failure, and toxic ingestion. It is a clue that further workup is needed.
How does low albumin change the anion gap?
The albumin level carries negative charge, so low albumin can lower the measured anion gap. In that case, a adjusted anion gap may better reflect the real acid-base status. Low albumin can hide an important elevation if the result is not corrected.
Can an anion gap that is normal still be abnormal in acid-base disorders?
Yes. A normal anion gap does not rule out an acid base disorder. Some forms of metabolic acidosis keep the gap normal because bicarbonate loss is balanced by chloride gain. That is why the result must be interpreted with the rest of the test results and the full clinical picture.