What Is the Anion Gap?
The anion gap is a derived value used to assist evaluate electrolytes in a blood chemistry panel. It gives clinicians and readers a quick way to assess acid-base balance by comparing the main measured positive and negatively charged particles in the blood.
In practical terms, the anion gap helps estimate the amount of unmeasured anions in the bloodstream. It is not a direct lab measurement. Instead, it is a result calculation based on common serum electrolytes reported on an electrolyte panel, especially sodium, chloride, and bicarbonate.
This makes the anion gap a useful diagnostic aid when reviewing lab results and deciding whether an acid-base disorder may be present. A quick blood test interpretation can show whether the pattern is consistent with a normal anion gap, high anion gap, or low anion gap.
Anion Gap Formula in mmol/L
The basic formula for anion gap in mmol/L is easy to use:
Anion gap = sodium - (chloride + bicarbonate)
Some laboratories also report the values in mEq/L, but for typical clinical use, the numeric result is usually the same when the electrolytes are measured in standard millimole-based reporting. That is why many people can use an anion gap calculator without worrying too much about the unit label, as long as the lab values match the calculator’s expected format.
The calculation uses the major measured ions:
- Sodium as the chief measured cation Chloride as a key measured anion Bicarbonate as another key measured anion
Because the calculation is based on measured ions, it helps identify variations in the balance of charged particles. That is why the anion gap is often reviewed alongside other serum chemistry findings when evaluating acid-base balance.
How to Work Out Anion Gap Step by Step
To determine anion gap properly, you need the specific serum sodium, serum chloride, and serum bicarbonate values from the matching lab draw if possible. If you use a calculator or doing the math by hand requires the same steps.
This is a basic workflow:
- Find the serum sodium value. Locate the serum chloride value. Locate the serum bicarbonate value. Add chloride and bicarbonate together. Subtract that total from sodium.
Sample calculation:
If the serum sodium is 140 mmol/L, the serum chloride is 104 mmol/L, and the serum bicarbonate is 24 mmol/L, then:
Anion gap = 140 - (104 + 24)
Anion gap = 140 - 128 = 12 mmol/L
This sample calculation shows why an anion gap calculator can be valuable: it minimizes arithmetic mistakes and offers quick clinical interpretation when reviewing electrolyte values.
Helpful tip: When comparing multiple lab panels, always verify that the same unit system is used and that the values come from the same blood chemistry panel.
Normal Anion Gap Values and Measurements
The normal range for anion gap is determined by the laboratory’s reference interval and the way the test is displayed. https://anion-gap-tool502.bearsfanteamshop.com/anion-gap-calculator-how-to-calculate-and-interpret-the-result In many settings, the typical reference range is approximately 8 to 12 mmol/L when potassium is not included, though some labs may use slightly different cutoffs.
Some labs report the result in mEq/L, and the number may appear nearly identical in routine use. Still, the best practice is to check the lab’s own reference interval rather than relying only on a generic range.
Why this matters:
- A value in the normal range does not always eliminate an important issue. A result outside the expected reference range may indicate a true acid-base problem or a lab-related issue. Interpretation should always include the full blood chemistry panel, not just a single value.
The phrase anion gap in mmol/L is common in clinical discussions because it clearly matches many modern lab reports. Whether you see mmol/L or mEq/L, the key is to apply the lab’s own reference interval for accurate comparison.
What Does a High Anion Gap Mean?
A elevated anion gap commonly means that extra acids are present in the blood, which can point toward acid-base imbalance. In this case, the body has more unmeasured anions than expected, frequently because of the buildup of acid byproducts.
Common causes of a increased anion gap include:
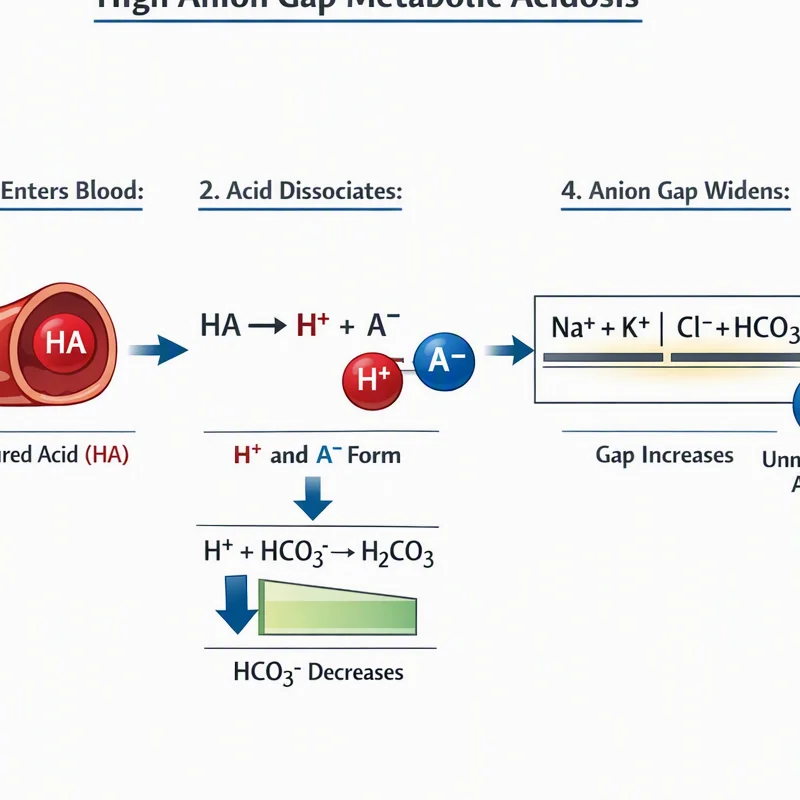
- Elevated lactate, when lactate rises because tissues are not using oxygen normally or because of other metabolic stress Ketone-related acidosis, which can occur when ketone bodies rise significantly Additional causes of acidosis that increase acid load
In clinical interpretation, the anion gap is one clue among several. A high result can support the idea of an acid-base disorder, but it does not identify the exact cause by itself. This is why clinicians look at the full picture, including symptoms, glucose, kidney function, and other lab results.
If you are using an anion gap calculator, a result above the lab’s reference range should prompt a close review of the rest of the electrolyte results and the patient’s context.
What Is the Meaning of a Low Anion Gap?
A reduced anion gap is less common than a raised one, but it can still be significant. One of the main explanations is hypoalbuminemia, because albumin is a negative-charged protein that plays a role in the equilibrium of measured and unmeasured ions.
Other possible reasons for a low anion gap include:
- Decreased albumin levels Laboratory error or testing issue More rarely, abnormal shifts in measured ions or proteins
Because laboratory error can sometimes cause an unexpectedly low result, it is often advisable to repeat the test or inspect the raw values before drawing conclusions. A single abnormal number should not be interpreted in isolation.
In many cases, the first question is whether the result is truly low or whether it needs to be adjusted for albumin. That leads directly to the idea of albumin correction.
How Albumin Influences the Anion Gap
Albumin correction is essential because serum albumin plays a major role in the reported anion gap. Because albumin is a negatively charged protein, lower albumin often decreases the apparent calculated anion gap even when the underlying acid-base balance has not changed much.
That is why clinicians sometimes calculate a corrected anion gap. It helps make the result more useful when serum albumin is low, especially in patients with chronic illness, inflammation, or poor nutrition.
A common approach is to adjust the anion gap upward when albumin is below normal. The exact correction formula can vary by institution, but the goal is the same: read the anion gap as if albumin were closer to a standard level.
Why it matters clinically:
- A low albumin level can make the anion gap seem deceptively normal or low. Corrected anion gap values can identify hidden metabolic acidosis. Albumin correction increases the accuracy of clinical interpretation.
When reviewing a result that seems inconsistent with the patient’s condition, checking serum albumin is often a helpful next step. This is especially useful when you are reviewing multiple lab results from the same blood chemistry panel.
When to Use an Anion Gap Calculator
An anion gap calculator is especially helpful when you want a fast and dependable result calculation from an electrolyte panel. It can save time and limit manual math errors, especially when multiple values must be checked in a short time.
You may want to use an anion gap calculator when:
- You are evaluating an electrolyte panel for signs of an acid-base disorder You need fast clinical interpretation of a blood chemistry panel You want to contrast reference range values across different lab reports You are determining whether an abnormal result may represent metabolic acidosis
It is especially helpful when you need to compare serum electrolytes across repeated tests or when you want to understand the relationship between the numbers and the underlying physiology. A calculator is a practical diagnostic aid, but the final meaning still depends on the full clinical context.
Common Errors When Calculating Anion Gap
Even though the formula is simple, there are several common mistakes that can affect blood test interpretation. Paying attention to details can enhance the accuracy of the calculation and the reliability of the result.
- Units: Make sure you are using the right unit system and comparing results in the same format. Potassium: Some formulas include potassium, while others do not. Using the wrong version can change the result. Measurement error: A specimen problem or analyzer issue can distort the numbers. Reference values: Always compare the result to the lab’s specific reference values, not just a generic range.
Another common issue is mixing results from different time points. If sodium, chloride, and bicarbonate were not measured from the same sample, the anion gap formula may not reflect the patient’s true status. That is why the best approach is to use the same serum chemistry set whenever possible.
In conclusion, keep in mind that the anion gap is only one part of a wider clinical interpretation. It should be considered alongside symptoms, follow-up testing when needed, and other markers relevant to pH balance.
FAQs
How do you calculate anion gap in mmol/L?
Use the anion gap formula: sodium - (chloride + bicarbonate). Enter the sodium level, serum chloride, and bicarbonate level values from the lab report, then take away the sum of chloride and bicarbonate from sodium. The final result is usually reported in mmol/L.
What’s the normal anion gap range in mmol/L?
The normal values depend on the lab’s reference span, but many labs use a reference range of about 8 to 12 mmol/L when potassium is not included. Always verify the specific lab report because the usual range can vary slightly.
Why is albumin correction important for anion gap?
Albumin adjustment matters because albumin is a major negatively charged plasma protein. When blood albumin is low, the anion gap may appear falsely low or normal. A adjusted anion gap gives a more accurate view of the acid-base status and improves interpretation.
What does a high anion gap indicate?
A high anion gap often points to acid buildup caused by extra acids or additional anions in the blood. Common causes include lactate buildup and ketoacidosis. It is a helpful clue, but it should always be interpreted with the full clinical picture.
Should potassium be included in the anion gap formula?
That depends on the formula used by the lab or calculator. Some versions include potassium, while many common clinical calculations do not. If you use an anion gap calculator, check whether the tool includes potassium so the final calculation matches the intended method and reference limits.