An Anion Gap Calculator is a practical tool for interpreting an anion gap value on a metabolic panel. It helps converting common laboratory values into a helpful diagnostic clue for reviewing acid-base balance, especially when a clinician is looking over an electrolyte panel for signs of metabolic acidosis or related acid-base disorder patterns.
Used correctly, the calculator does much more than produce a number. It helps link serum sodium, serum chloride, and serum bicarbonate to the broader picture of metabolic panel interpretation. That means it can support recognition of a high anion gap, a low anion gap, or results that need verification with additional testing.
What the Anion Gap Measures
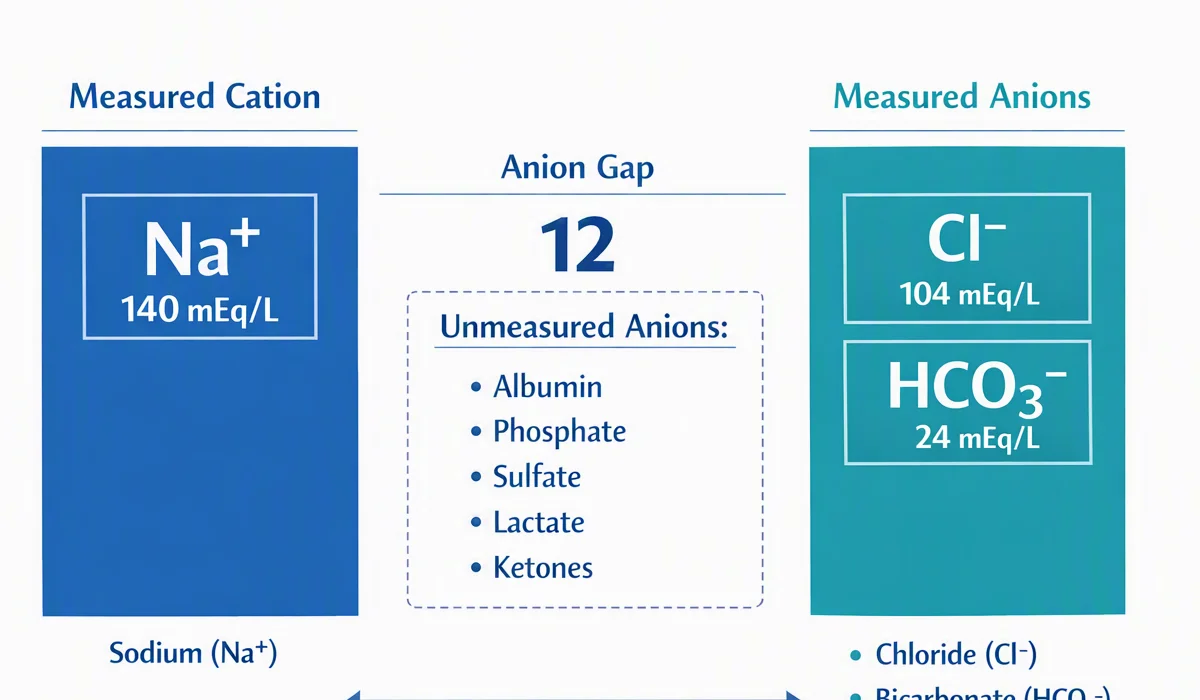
The anion gap is an estimate of the difference between measured positive and negative electrolytes in the blood. In routine practice, it mainly describes the relationship between sodium, chloride, and bicarbonate. Because not all charged particles are directly measured, the anion gap provides an indirect picture at the presence of unmeasured ions and unmeasured anions.
In simple terms, the anion gap helps identify whether something is affecting acid-base balance. A normal result suggests that the measured cations and anions are in expected proportion, while an abnormal result may point to an underlying acid-base disorder. This is why the anion gap is a standard part of metabolic panel interpretation in many settings.
Although the number is derived from routine chemistry tests, its clinical significance is much more extensive than the formula itself. A change in the anion gap can be a diagnostic clue that prompts a more detailed metabolic acidosis evaluation, review of medications, or follow-up testing such as a blood gas.
How to Work Out the Anion Gap
An Anion Gap Calculator simplifies the process of calculate anion gap from findings from a basic metabolic panel or comprehensive metabolic panel. The standard anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Some labs may use different formulas, especially if potassium is included. But, the sodium-based version is the most common in everyday interpretation.
To use the calculator, enter the patient’s serum sodium, serum chloride, and serum bicarbonate. The result estimates the gap between measured cations and anions. If the number is higher than expected, it may indicate an increased amount of unmeasured anions. If it is lower than expected, the result may reflect low albumin, lab variation, or another less common cause.
The calculator is especially helpful when reviewing a electrolyte panel efficiently. For example, a low bicarbonate with normal chloride may point toward metabolic acidosis, while a low bicarbonate with a markedly elevated anion gap suggests a high gap acidosis.
It is important to remember that the calculator is only one step in clinical reasoning. It aids, but does not replace, a full assessment of symptoms, history, medications, and the rest of the lab pattern.
Normal Anion Gap Values and Factors That Affect Them
The normal range for the anion gap is determined by the assay method and the lab’s reference interval or lab interval. As different laboratories measure ions differently, a result that is “normal” in one setting may sit slightly outside the range used elsewhere.
Such differences is one reason clinicians should always interpret the number in context rather than relying on a single cutoff. The lab’s stated reference range is the most useful guide for that specific result.
Albumin has a major effect on the anion gap because it is a negatively charged protein and contributes substantially to the pool of unmeasured anions. When albumin is low, the anion gap may appear falsely reduced even if an acid-base problem is present. This is where correction for albumin becomes important.
An corrected-for-albumin or anion gap corrected for albumin estimate adjusts for reduced albumin so the result better reflects the true acid-base picture. In practical terms, if albumin is low, the corrected value may reveal a hidden elevation that would otherwise be missed. This helps reduce the risk of a falsely low anion gap.
Albumin adjustment is especially helpful when the patient has illness, inflammation, malnutrition, liver disease, or fluid overload—situations where albumin may be below the usual range. In those cases, the raw result may not fully represent the patient’s actual acid-base status.
High Anion Gap Metabolic Acidosis Causes
A high anion gap is most often associated with metabolic acidosis. This occurs when acids collect in the blood and increase the amount of unmeasured negative ions. The bicarbonate level commonly falls because it is being utilized to buffer acid, and the anion gap goes up as a result.
Frequent causes of elevated anion gap include:
- Lactate buildup, which can occur when tissues are not well perfused or under severe metabolic stress Ketoacidosis, including alcoholic or alcoholic forms Kidney failure, where the kidneys cannot clear acid effectively Exposure to certain toxins or drugs that create or hold onto acids
Lactic acidosis is a common cause of increased gap results and commonly signals tissue hypoxia, sepsis, or other conditions that reduce oxygen delivery or utilization. Ketone-related acidosis often appears with high ketones and may be seen in diabetes, prolonged fasting, or heavy alcohol use. Renal failure adds to the problem by reducing acid excretion and allowing acid metabolites to build up.
When the calculator returns a elevated result, the next step is not just to label it abnormal. The key is to relate it to the patient’s overall clinical picture. For example, a low bicarbonate with a high anion gap clearly suggests a high gap acidosis pattern, but the exact cause still requires targeted evaluation.
In many cases, the anion gap is a useful starting point for a systematic workup. Depending on the context, that may include lactate, ketones, creatinine, toxicology testing, and a blood gas to assess pH and compensation.
Low Anion Gap Reasons and Clinical Importance
A decreased anion gap is less common than a high one, but it can be medically significant. The most frequent explanation is low albumin, since albumin is a major unmeasured anion. When albumin decreases, the measured gap may decline even if the patient’s acid-base status https://anion-gap-reference112.timeforchangecounselling.com/understanding-the-anion-gap-in-shock is still unchanged.
Other important causes include multiple myeloma, lithium exposure, and paraproteinemia. These conditions can decrease the calculated gap by adding positively charged proteins or cations into the system, changing the balance of measurable ions.
Multiple myeloma and other paraproteinemia states can generate abnormal proteins that influence the result. This is why an unexpectedly low number should not be overlooked automatically. It can be a clue to a wider diagnostic process, especially if the patient also has anemia, kidney dysfunction, bone pain, or elevated total protein.
Lithium is another notable cause because it is a cation that can affect the calculation. In the appropriate clinical setting, a low anion gap may provide an early warning sign of lithium effect or toxicity.
As with a high result, a low value requires interpretation. A low gap may be due to true disease, but it can also reflect a measurement issue or a misleading result from low albumin. Correcting for albumin and reviewing the full chemistry panel supports interpretation.
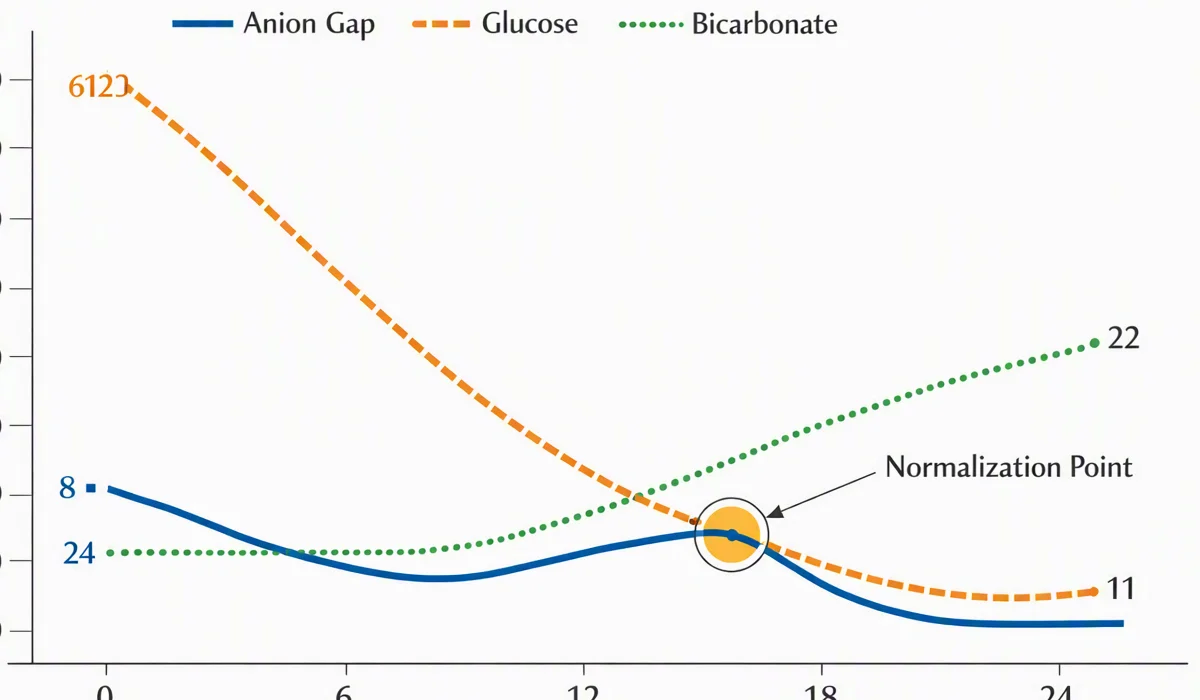
Interpreting Results for a Metabolic Panel
Accurate metabolic panel interpretation starts with the pattern, not the number alone. The anion gap should be interpreted alongside acid-base status, sodium, chloride, bicarbonate, and the patient’s clinical status. A complete interpretation often reveals whether the problem is an electrolyte disturbance, an acid accumulation state, or a mix of both.
For example, a low bicarbonate with elevated chloride may indicate a normal-gap acidosis with a shift in chloride. In that scenario, the body may be exchanging bicarbonate loss for chloride gain, keeping the anion gap within range even though acidosis is present. By contrast, low bicarbonate with a high anion gap points more toward acid accumulation from causes such as lactic acidosis, ketoacidosis, or renal failure.
The chloride shift is significant because chloride often rises as bicarbonate falls in certain forms of acidosis. That means a patient can have clear acid-base disruption even when the anion gap is not elevated. This is why the calculator should be used as part of a broader review of the entire electrolyte panel.
One practical approach is to interpret results in this order:
- Check sodium, chloride, and bicarbonate for clear abnormalities Use the Anion Gap Calculator to identify a high or low pattern Evaluate whether albumin may require correction Compare the pattern with likely causes and symptoms Determine whether additional testing, including a blood gas, is needed
This method improves the chance of identifying the correct acid-base abnormality and makes the result more useful than a standalone calculation. The anion gap is best viewed as a useful bridge between raw lab values and a diagnosis that explains what is happening physiologically.
Constraints, Common issues, and When to Repeat
Despite this a well-used calculator has constraints. One common issue is testing error. A specimen problem, sample contamination, or analyzer issue can produce a misleading value. When the number does not fit the clinical picture, retesting is often the right next step.
Another pitfall is failure to account for unmeasured anions or protein-related effects. If albumin is low, the raw number may underestimate the severity of the underlying disturbance. If a patient has abnormal proteins or unusual cation exposure, the result may be shifted in the opposite direction.

A blood gas can be useful when the chemistry panel and symptoms do not align. It provides pH and respiratory compensation data, which can clarify whether the issue is truly metabolic, respiratory, or mixed. In patients with severe illness, the blood gas may also help confirm the urgency of the finding.
Repeat the result when:
- The number is inconsistent with the patient’s condition The sample may have been mishandled Albumin is abnormal and correction has not been applied There is concern for a hidden acid-base problem Treatment has been started and response needs confirmation
In short, the calculator is valuable, but it should not be treated as the final answer. A careful recheck can prevent misclassification and help distinguish a true abnormality from a transient or artifactual finding.
Common Questions
What is an Anion Gap Calculator used for?
An Anion Gap Calculator is used to help interpret a metabolic panel by estimating the difference between measured electrolytes and identifying possible acid-base abnormalities. It is especially helpful for spotting a high anion gap or decreased anion gap pattern and for guiding next-step clinical reasoning.
How do you calculate the anion gap from a metabolic panel?
The standard formula for the anion gap is sodium - (chloride + bicarbonate). This calculation uses values from a BMP or comprehensive metabolic panel. Many clinicians use a calculator to make this faster and reduce arithmetic errors.
How to understand a normal anion gap range?
The lab reference interval can vary by laboratory because various analyzers and techniques can alter the result. This is why you should use the lab’s stated normal range or lab reference range rather than choosing one single cutoff.
Why would the anion gap be high or low?
A elevated anion gap often indicates metabolic acidosis from causes such as elevated lactate, ketone-related acidosis, or kidney failure. A decreased anion gap is often linked to decreased albumin, but it can also occur with myeloma, lithium therapy, or abnormal proteins in the blood.
Is albumin adjustment necessary when interpreting the anion gap?
Absolutely, when blood albumin is low, albumin correction can refine interpretation and reveal a more accurate albumin-adjusted anion gap. This matters because hypoalbuminemia can make the gap look lower than it really is, leading to a spuriously low anion gap and a missed diagnostic clue.