An anion gap calculator is a practical diagnostic tool for understanding blood chemistry results. It assists translate raw blood test values into a more understandable picture of acid-base balance, especially when a metabolic disturbance may be present. By comparing measured electrolyte levels such as sodium, chloride, and bicarbonate, the calculator calculates the anion gap value, which can point to hidden unmeasured anions and inform clinical interpretation.
With correct use, the calculator does more than calculate anion gap. It aids review of a laboratory result from a basic metabolic panel or a comprehensive metabolic panel, and it can help identify whether the pattern fits a normal anion gap, high anion gap, or low anion gap state. That distinction matters because it influences how clinicians think about metabolic acidosis, renal function, and the likely cause of an abnormal serum chemistry profile.
How the Anion Gap Is Measured
The anion gap is a calculated value that shows the gap between measured positively charged and negative particles in the blood. In everyday practice, it is mainly derived from sodium, chloride, and bicarbonate. As routine testing does not measure all ions, the anion difference can suggest the presence of additional acids or other ions that are not directly reported.
This renders the anion gap useful for understanding acid-base status. If the body accumulates acids, the measured bicarbonate often falls while the gap rises, suggesting extra anion concentration from substances such as lactate, ketones, or toxins. In that sense, the number acts as a window into the body’s overall acid-base disorder rather than a single diagnosis.
The test is usually interpreted with other parts of blood chemistry, including kidney markers and electrolytes. Since these values are commonly available in a metabolic panel, the anion gap becomes an effective way to spot potential problems quickly.
In What Way the Anion Gap Calculator Functions
The anion gap calculator uses a simple equation based on a blood chemistry panel or serum chemistry report. Many calculators ask for sodium, chloride, and bicarbonate, and others also allow entry of potassium or albumin. The result can indicate whether the laboratory result falls within the expected reference interval or suggests a shift in acid-base status.
For most users, the value is easiest to understand as a quick check of the balance between measured cations and measured anions. If chloride and bicarbonate shift in opposite directions, the gap changes. That pattern can be a clue that the body is responding to a metabolic disturbance or that something else is contributing to the chemistry profile.
In practical terms, the calculator helps clinicians and other readers:
- Review a metabolic panel for an unexplained abnormality. Spot possible metabolic acidosis when the chemistry pattern is concerning. Compare results over time to see whether the anion gap value is shifting. Support clinical interpretation when symptoms and lab findings need to be connected.
Because https://anion-gap-test559.swiftnestly.com/posts/understanding-delta-ratio-in-anion-gap-assessment the tool is based on routine blood test values, it is especially helpful when a quick interpretation is needed before additional testing is ordered.
Anion Gap Formula and Normal Ranges
The classic anion gap formula is given as:
Anion gap = Sodium − (Chloride + Bicarbonate)
Certain formulas include potassium, but most current approaches leave it out because its contribution is small. Whether potassium is used or not the purpose is still the same: to determine the difference between the major measured ions and spot possible unmeasured anions.
The normal range depends on the method used by the laboratory and whether the value has been adjusted for albumin. Various analyzers and reporting standards can shift the reference interval, so it is important to interpret the number with the actual lab report in mind. What looks borderline in one setting may be normal in another.
It is equally important to know albumin contributes significantly to the anion gap. Because albumin is a negatively charged protein, changes in serum albumin can alter the value even when acid-base physiology is otherwise unchanged. For that reason, many clinicians consider whether to correct for albumin before drawing conclusions.
In general, the key question is more than just whether the number is above or below a textbook range, but whether it fits the rest of the serum chemistry, symptoms, and overall acid-base balance.
Elevated Anion Gap vs Reduced Anion Gap
A high anion gap usually suggests that undetected acids are present in the blood. This often points toward metabolic acidosis, especially when bicarbonate is lowered. The rise happens because extra acid anions, which are not directly included in the routine calculation, contribute to the pool of unmeasured anions.
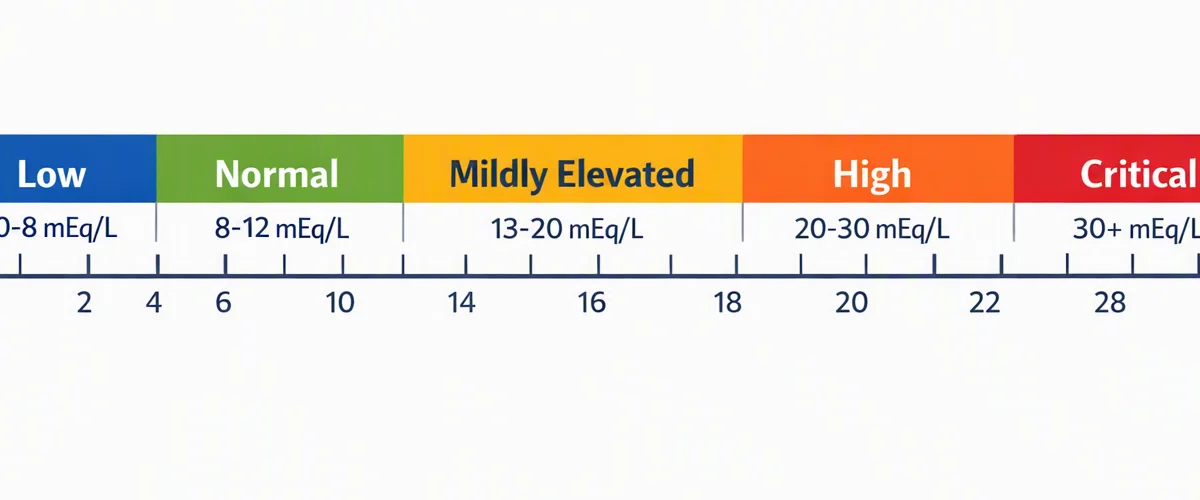
A reduced anion gap is less common, but it still counts in laboratory interpretation. It may reflect low albumin, analytical issues, unusual protein levels, or other shifts in ion balance. While a low value does not always signal a serious problem, it should not be ignored if it keeps appearing or fits the broader clinical picture.
These patterns help shape the next step in clinical interpretation. A high value often leads the evaluator to think about acid accumulation, while a low value pushes attention toward protein changes, possible measurement issues, or less common causes of electrolyte distortion.
In either case, the anion gap is not a final diagnosis. It is a clue that helps organize the differential diagnosis and focus attention on the most likely causes of the abnormal chemistry pattern.
Frequent Causes for an High Anion Gap
A number of issues can raise the anion gap. Among the frequent are lactic acidosis, ketoacidosis, kidney failure, and toxic ingestion. Every one of these can worsen acid load or decrease the body’s ability to clear acids, causing a elevated anion gap value.
Lactic acidosis can occur when tissues do not get or use oxygen properly, causing lactate to rise. Ketoacidosis happens when ketones build up, often in contexts of insulin deficiency, starvation, or severe illness. Kidney failure can lower acid excretion, allowing acids to build up and changing renal function markers alongside the chemistry profile.
Toxic ingestion is another important category because certain substances can create a marked high anion gap. In these cases, the chemistry pattern may be a important early clue, especially if the patient’s symptoms are nonspecific. This is why the calculator is best used as part of larger clinical interpretation rather than as a stand-alone number.
A normal gap does not rule out illness, and an elevated gap does not identify the exact cause. It simply limits the field by pointing toward a class of disorders that disrupt acid-base status.
How Serum Albumin Impacts the Calculation
Albumin has a major influence on the anion gap because it is one of the main negatively charged proteins in the blood. When serum albumin is decreased, the measured gap may appear lower than expected even if there is still an underlying acid problem. This condition, known as hypoalbuminemia, can obscure a true high anion gap state.
That is why many clinicians use albumin correction to determine a corrected anion gap. The goal is to refine the result so the interpretation better reflects the patient’s actual acid-base condition. In other words, the correction helps the calculator better correct for albumin and enhances the accuracy of the result.
This step is especially important when the raw anion gap seems within range or only slightly abnormal but the patient’s symptoms suggest a more significant metabolic problem. A low serum albumin level can reduce the gap enough to hide clinically relevant changes in blood chemistry.
Because albumin is such a important modifier, any accurate interpretation should consider the protein level alongside the electrolyte values. The corrected anion gap is often more helpful than the unadjusted number when hypoalbuminemia is present.
When to Retest or Validate the Value
Not every unusual result means there is a genuine bodily problem. Sometimes repeat testing is needed to confirm the result. A one-time odd value may result from laboratory error, sample handling issues, or transient changes in electrolyte disturbance.
Retesting is especially useful when the value does not fit the patient’s symptoms or the rest of the chemistry panel. If the numbers appear inconsistent, the best next step may be to repeat the blood analysis analysis and compare it with the broader medical context.
Common examples of situations that may justify confirmation include:
- A value that is unexpected for the patient’s condition. A abrupt change from prior blood test values. A near-normal abnormality without supporting symptoms. Concern that the sample may have been affected by collection or processing issues.
Checking the value helps avoid overinterpreting a single number and supports more reliable clinical assessment.
How Clinicians Interpret the Result
Clinicians do not read the anion gap in isolation. They combine it with the full acid-base disorder picture, including the blood gas analysis, the chemistry panel, and the patient’s overall status. The goal is to decide whether the pattern reflects a genuine disturbance in acid-base balance and what type of process is most likely responsible.
A high gap with low bicarbonate often supports acidic metabolic state, but the cause still needs to be identified. A normal gap can coexist with illness, especially if the abnormality is due to a different mechanism such as diarrhea, saline-related shifts, or an early process not yet reflected in the chemistry values. A low gap may prompt review of albumin, repeat testing, and consideration of less common explanations.
In this setting, the anion gap becomes part of the differential diagnosis. It helps clinicians separate broad groups of disease, decide whether additional testing is needed, and determine whether the issue is primarily metabolic, renal, toxicologic, or related to protein changes.
That is the real-world value of the anion gap calculator: it turns routine laboratory chemistry data into a structured interpretation that supports decision-making. The number itself is important, but the pattern around it often matters more.
FAQ About the Anion Gap
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the anion gap from a blood test such as a basic metabolic panel or comprehensive metabolic panel. It is used to evaluate acid-base status, recognize possible metabolic acidosis, and inform clinical interpretation of blood chemistry results.
What is the normal anion gap range in blood chemistry?
The reference range differs by laboratory method, analyzer, and whether albumin is considered. Because of that, there is not one standard normal range. The best approach is to compare the result with the lab’s own reference interval and the rest of the serum chemistry report.
Why is a high anion gap important?
A high anion gap is important because it often signals extra acids in the blood, which can indicate metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, kidney failure, and toxic ingestion. It is a clue that more evaluation may be needed.
How does low albumin affect the anion gap?
Low serum albumin can make the anion gap look artificially low. This is why hypoalbuminemia often leads clinicians to use albumin correction and calculate a corrected anion gap. Adjusting for albumin can reveal an underlying abnormality that the uncorrected value hides.
Can a typical anion gap also mean a health concern?
Indeed. A typical anion gap does not rule out illness. Some conditions lead to a normal anion gap acid-base imbalance, and early disease may not yet alter the number much. The result should always be interpreted in medical context with other lab chemistry findings and, when needed, additional tests for medical guidance.