What Is the Anion Gap?
The anion gap is a derived value that guides clinicians understand acid-base balance by comparing measured serum sodium against measured serum chloride and serum bicarbonate. It is not a directly measured lab result. Instead, it is a useful diagnostic marker taken from a standard chemistry panel, often supported by an anion gap calculator for quick clinical interpretation.
At a fundamental level, the anion gap reflects the disparity between the positively charged ions and the negatively charged ions reported in routine serum electrolytes. Because the body must remain electrically balanced, this gap can reveal hidden acids in the blood when the balance shifts. That is why the anion gap is often part of the evaluation for metabolic acidosis and other acid-base disorder patterns.
The commonly used calculation formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
When the value is elevated, it often indicates unmeasured acids in the bloodstream. When it is normal, it does not always mean the patient is stable, but it does narrow the differential diagnosis. In practice, the anion gap is one of the most useful tools for reviewing laboratory values in the setting of illness, dehydration, or suspected metabolic derangement.
How come the Anion Gap Calculator Is Important in diabetic ketoacidosis
diabetic ketoacidosis is a well-known cause of elevated anion gap metabolic acidosis. In this condition, the body cannot use glucose effectively because of insulin deficiency, so it begins metabolizing fat for fuel. This process produces ketone compounds, including beta-hydroxybutyrate, which collect and drive an increased anion gap.
As ketones accumulate, they increase ketone buildup and use up bicarbonate, which contributes to falling bicarbonate and a declining serum bicarbonate level. The result is worsening blood acidity and a marked disturbance in the acid-base balance. A patient with DKA may also have dehydration, electrolyte imbalance, and increasing severity of acidosis, all of which affect the clinical picture.
The gap helps distinguish DKA from other causes of metabolic acidosis. It is especially useful when symptoms are nonspecific or when a blood gas has not yet been obtained. Together with glucose, ketones, and the electrolyte panel, it helps confirm the diagnosis and track how severe the metabolic derangement is.
Because DKA can develop rapidly, an anion gap calculator can be a useful way to read the chemistry profile in real time. It does not take the place of clinical judgment, but it aids better clinical interpretation when reading serum electrolytes, blood gas results, and ketone testing together.
How to Calculate the Anion Gap
The standard anion gap formula uses the sodium level, chloride level, and bicarbonate level values from an electrolytes panel. Most formulas leave out potassium, although some clinicians consider it in specific contexts. A standard calculation is:
Anion gap = sodium - (chloride + bicarbonate)
For example, if serum sodium is 140, serum chloride is 100, and serum bicarbonate is 12, the anion gap is 28. That degree of elevation strongly points to an acid load from unmeasured anions, such as ketones in DKA.
However, the raw number may be inaccurate when albumin is low. Albumin is a major unmeasured anion, so low albumin can make the anion gap look falsely normal or only mildly elevated. That is why a corrected anion gap is often used when interpreting metabolic acidosis. This adjustment increases accuracy, especially in critically ill patients, where protein levels may be altered.
Using an anion gap calculator can simplify the process, especially when it includes albumin correction. A corrected value is often more useful for determining whether the patient has ongoing acid retention or whether the measured gap is being masked by hypoalbuminemia. This is important in both diagnosis and monitoring trend over time.
In DKA, the calculation should always be interpreted alongside the blood gas, potassium, glucose, ketones, and the overall clinical picture. The number alone is useful, but the pattern matters more than a single result.
Typical Anion Gap Values in DKA
A normal anion gap usually lies within the laboratory expected range, though exact thresholds vary by method and instrument. Many labs report values near 8 to 12 mEq/L, but the accepted range depends on the local blood chemistry system and the lab’s calibration. Because of this, clinicians should always use the reference interval from the reporting laboratory.
In elevated anion gap metabolic acidosis, the anion gap is elevated because unmeasured acids are present in excess. DKA is one of the classic examples. The larger the gap, the more likely there is significant ketone accumulation, though the degree of elevation does not always perfectly match symptom severity.
Blood chemistry in DKA often shows:
- High glucose Decreased serum bicarbonate Differing serum chloride Shifts in potassium Increased ketones, especially beta-hydroxybutyrate
It is essential to remember that the anion gap is a sign, not a diagnosis by itself. DKA is usually confirmed by the combination of hyperglycemia, ketones, and metabolic acidosis. When considered in context, the anion gap helps identify the presence of an acid burden and guides the urgency of treatment.
How the Anion Gap Changes During DKA Treatment
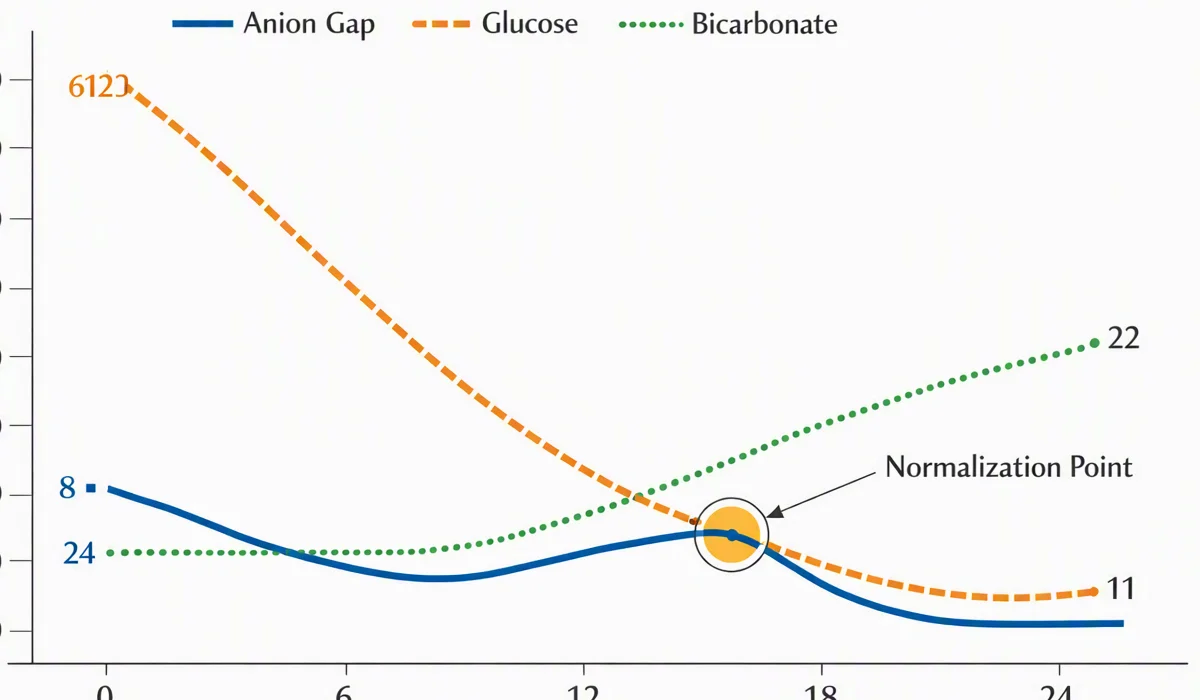
As treatment begins, the anion gap should generally drop if the therapy is successful. This shift reflects ketone clearance, which occurs as insulin therapy ends ongoing ketone production and helps the body use glucose again. Intravenous fluids also enhance circulation, reduce dehydration, and support renal clearance of acids and ketones.
In the recovery phase, serum bicarbonate typically rises as acid production falls and buffering gets better. This is often described as bicarbonate recovery. A closing anion gap is one of the clearest signs that the metabolic acidosis from DKA is improving.
That said, the anion gap may not normalize immediately, especially if ketone bodies remain in circulation or if treatment has only partially treated the underlying problem. Monitoring trend is more helpful than relying on a single repeat value. Clinicians often follow the electrolyte panel and blood gas together to assess treatment response.
It is also common for potassium to shift during therapy. Even if potassium is normal or high at presentation, it may fall after insulin and fluids begin. This does not directly determine the anion gap, but it is a critical part of the overall acid-base and electrolyte picture.
In short, falling anion gap values usually indicate that treatment is working. Increasing or persistent values suggest ongoing acid generation, incomplete ketone clearance, or another cause of acidosis that deserves review.
Anion Gap vs. Bicarbonate: What is the Difference?
The anion gap and bicarbonate are associated but not equal. Bicarbonate measures one element of the body’s acid-buffering system, while the anion gap indicates the presence of extra acids. Both are essential to understanding acid-base status, but they raise different issues.
A decreased bicarbonate level tells you that acidosis is present or that buffer has been depleted. A elevated anion gap tells you that the acidosis is probably caused by unmeasured ions such as ketones, lactate, or toxins. In DKA, both are often abnormal at the same time.
This difference matters because other acid-base disorders can look similar at first glance. For example, lactic acidosis can also raise the anion gap, and a patient may have both DKA and lactic acidosis at the same time. Blood gas results, lactate testing, and the clinical context help sort out the cause.
Think of bicarbonate as the “what is low?” number and the anion gap as the “what is accumulating?” number. Combined they provide a much more complete view of the patient’s metabolic state than either value alone. This is why the anion gap calculator is so useful in practice: it helps link the chemistry profile to the underlying physiology.
When a Standard Anion Gap May Not Exclude DKA
A normal anion gap does not always rule out DKA. This is a major pitfalls in diagnostic interpretation. A patient can have a overlapping acid-base disorder, where one process elevates the gap while another lowers it. As a result, the final number may appear falsely normal.
One common reason is hyperchloremia. During treatment or due to fluid shifts, chloride can rise and offset the unmeasured anions, producing hyperchloremic acidosis. In this setting, ketones may still be present, but the gap no longer appears elevated in the expected way.
The delta gap can help identify this problem. It contrasts the change in anion gap to the change in bicarbonate and helps show whether more than one acid-base process is occurring. If the relationship does not fit typical DKA, a combined disorder should be considered.
Ongoing ketosis is another clue. A normal gap may coexist with ongoing ketone production, especially if treatment has started but has not fully corrected the underlying insulin deficiency. That is why ketones, blood gas, and electrolyte values all matter together. A single normal gap should never end the evaluation when the clinical picture still suggests DKA.
Frequent Errors In Interpreting the Anion Gap
A typical error is forgetting albumin correction. Hypoalbuminemia can mask a true anion gap elevation and cause underestimation of the severity of metabolic acidosis. This is especially relevant in critically ill patients or those with poor nutrition, inflammation, or prolonged illness.
Another error is assuming all elevated gaps is DKA. While DKA is a major cause, other problems such as lactic acidosis, kidney failure, or toxin exposure can also increase the gap. Careful clinical interpretation is required to identify the true cause of the acid-base disorder.
Differences in lab methods also matters. Different laboratories may use slightly different methods, producing different reference interval cutoffs. For this reason the same patient can appear to have a different gap depending on where the blood chemistry is processed.
A further issue is ignoring broader electrolyte imbalance. Sodium, chloride, bicarbonate, and potassium all affect the interpretation. If one value is shifting because of fluids, renal function, or treatment, the anion gap may change in ways that reflect therapy rather than disease progression.
Finally, clinicians sometimes rely too heavily on the number alone. A good diagnostic interpretation requires the anion gap, ketones, glucose, blood gas, lactate, albumin, and the clinical presentation. The anion gap calculator is especially helpful when it is used as part of that larger assessment rather than as a stand-alone answer.
FAQ About the Anion Gap in DKA
What does a high anion gap suggest in diabetic ketoacidosis?
A high anion gap in diabetic ketoacidosis usually means that unmeasured acids, mainly ketone bodies such as beta-hydroxybutyrate, are accumulating in the blood. This pattern supports high anion gap metabolic acidosis and helps confirm the diagnosis when combined with glucose, ketones, and blood gas results.
What is the usual anion gap range?
The normal anion gap range depends on the laboratory reference interval, but many labs report a value roughly around 8 to 12 mEq/L. The exact cutoff can vary because of lab methods, so the reporting lab’s range should always be used when interpreting serum electrolytes.
How do you work out the anion gap with albumin adjustment?
You first compute the usual anion gap using sodium minus chloride plus bicarbonate. Then you modify for albumin because low albumin can hide a true elevation. A corrected anion gap gives a more precise estimate of the acid burden when albumin is low, improving clinical interpretation.
Can diabetic ketoacidosis happen with a normal anion gap?
Yes. DKA can sometimes present with a normal anion gap if there is a mixed acid-base disorder, hyperchloremic acidosis, or partially treated ketosis. Persistent ketosis may still be present even when the gap is no longer elevated, so the full electrolyte panel and blood gas should be reviewed.
How does the anion gap change after DKA treatment starts?
As insulin therapy and intravenous fluids begin taking effect, the anion gap usually falls because ketone clearance improves and bicarbonate recovery begins. A falling gap is a useful sign of treatment response, but the trend should be interpreted alongside potassium, https://anion-gap-calculator330.image-perth.org/how-to-calculate-anion-gap-in-mmol-l ketones, and other laboratory values.