What Is the Anion Gap?
The anion gap is a calculated measurement used to examine electrolytes and the body’s acid-base balance. It estimates the difference between the main recorded cations and opposing ions in the blood, especially sodium and chloride, along with bicarbonate. Since some ions are not directly measured on a standard blood chemistry panel, the anion gap aids in spot changes in anion concentration that may point to a metabolic disorder or other acid-base disorder.
Clinicians often apply the anion gap as a diagnostic indicator and a screening tool during patient evaluation. It does not provide a diagnosis by itself, but it can show that something is affecting serum levels and overall chemical balance. The key idea is simple: if the gap is elevated or reduced than expected, the blood test results may need closer review in clinical interpretation.
At its core, the anion gap reflects the presence of unmeasured anions in the blood. In many cases, those unmeasured ions become more relevant when the body is dealing with an acid load, kidney problems, or shifts in proteins such as albumin.
Anion Gap Calculator Formula
An anion gap calculator typically uses a basic formula using common laboratory values. The most common calculation is:
Anion gap = Serum sodium − (Serum chloride + Serum bicarbonate)
This calculation formula evaluates measured sodium with the sum of bicarbonate and chloride. The result helps show whether there may be an acid buildup or unusual ions affecting the blood. Because the formula relies on common test values, it is easy to apply once the values are available from a lab report.
Some labs and clinicians may use a somewhat different version that includes potassium, but the sodium-based version is the standard in everyday practice. When using any anion gap calculator, it is important to understand which lab reference standard is being used so the result is read accurately.
The formula is useful because it turns a few routine numbers into a practical medical assessment of electrolyte balance. A high or low result can suggest an electrolyte imbalance that deserves attention, especially if the patient has symptoms or abnormal blood test results.
How to Calculate Anion Gap Step by Step
To perform the calculation, beginning with the values from the blood chemistry panel:
- Serum sodium Serum chloride Serum bicarbonate
Then use the formula:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
Below is a straightforward example. If serum sodium is 140 mEq/L, serum chloride is 104 mEq/L, and serum bicarbonate is 24 mEq/L, the calculation is:
140 − (104 + 24) = 140 − 128 = 12 mEq/L
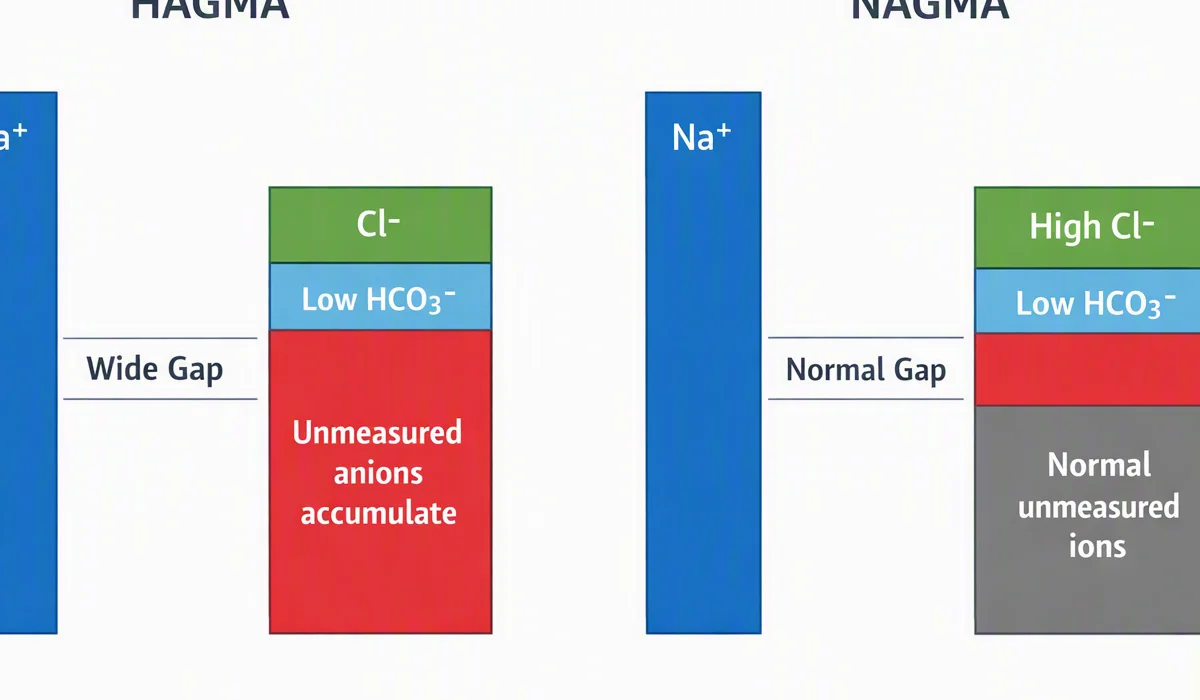
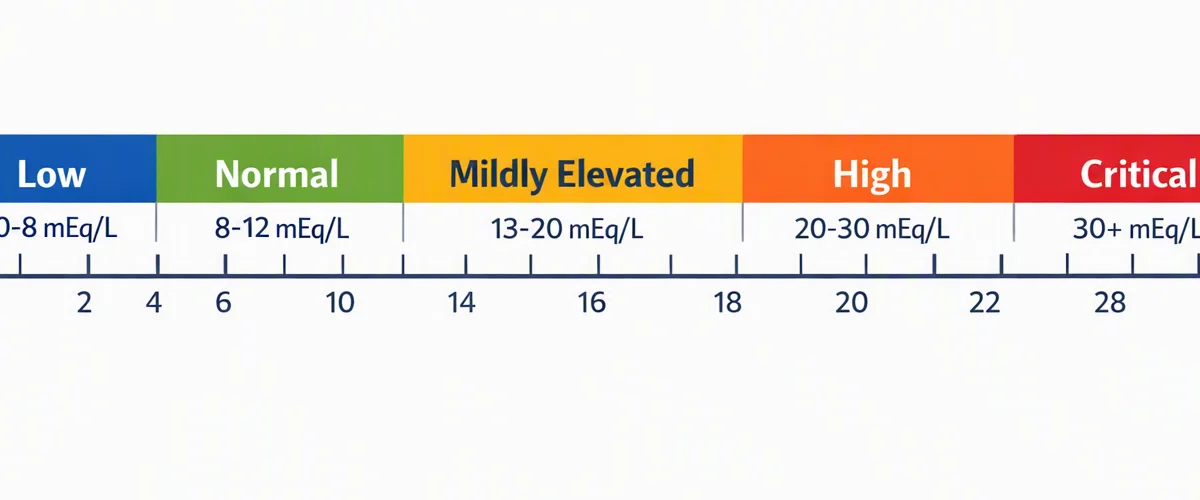
That value may fall within the expected normal range depending on the laboratory measurement method. The units are usually expressed in mEq/L. Because different instruments and lab methods can produce slightly different results, the exact reference range should always be checked against the reporting laboratory.
When reviewing the result, the number alone is not enough. The broader interpretive context should be considered, including symptoms, medications, kidney function, and whether there is evidence of metabolic acidosis or another acid-base disorder.
Normal Anion Gap Range and Units
The expected range for anion gap depends on the laboratory and the measurement method used. Many labs report a benchmark range that is roughly in the low numbers to low teens when measured in mEq/L. However, there is no single universal cutoff that applies to every lab because lab results can vary based on technology and calibration.
That is why it is best to interpret the result alongside the lab’s own reference range. A value that appears borderline in one setting may be normal in another. Also, different formulas may produce slightly different totals, which can affect how a result is categorized.
For practical use, the anion gap should be viewed as a trend as well as a single number. Repeated changes in the result may be more meaningful than one isolated value, especially if the patient’s serum levels are shifting over time.
Why a Elevated Anion Gap Signifies
A elevated anion gap often implies that extra acids are accumulating in the body, which can point in favor of an acid-base imbalance. In this setting, the blood contains additional extra negative ions that are not captured by the routine electrolyte panel. This is why the result is such a useful diagnostic indicator in a medical assessment.
Frequent causes include acidosis from lactate buildup, where lactic acid rises during poor tissue oxygenation, shock, or severe illness, and ketone-related acidosis, where ketones accumulate, often in diabetes, starvation, or alcohol-related states. Both conditions create an acid load that increases the gap.
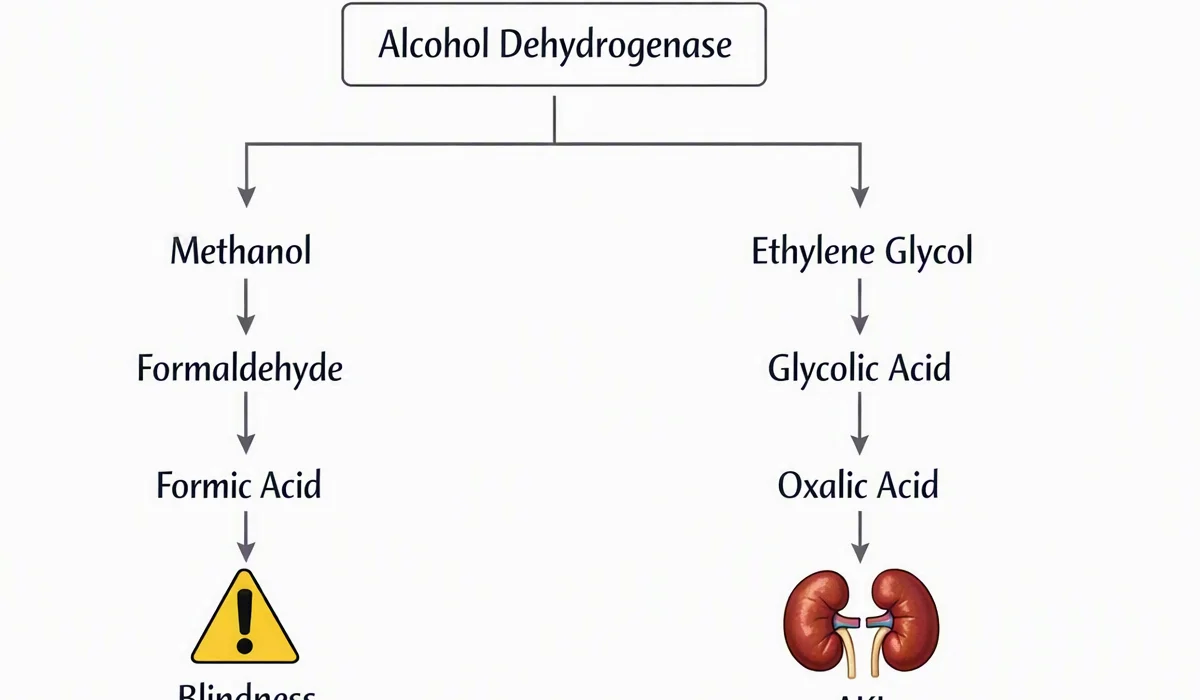
A high result may also be seen in renal failure, because the kidneys may not clear acids effectively. In some cases, a poison ingestion can raise the anion gap as well. The pattern should always be matched with symptoms, other lab data, and the overall clinical interpretation.
In short, a high anion gap does not tell you the exact cause, but it does alert clinicians to a likely metabolic disorder affecting acid handling or electrolyte balance.
What the Low Anion Gap Signifies
A low anion gap is not as common than a higher value, but it can still be important. One key cause is hypoalbuminemia, because albumin is a negatively charged protein that helps form the measured balance of ions. When albumin falls, the gap may decrease even if the underlying acid-base status has not shifted significantly.
Another possible explanation is lab error. Since the calculation depends on three distinct measurements, any mistake in serum sodium, serum chloride, or serum bicarbonate can alter the final result. That is why a very unexpected low value often deserves repeat testing or a careful review of the original blood test results.
Occasionally, a low result may reflect unusual proteins or other analytical issues. Because the number can be influenced by so many variables, it should be interpreted as part of the full clinical interpretation rather than as a standalone finding.
Modified Anion Gap & Albumin Correction
Because albumin creates a significant effect on the anion gap, healthcare professionals may use an albumin correction to calculate a corrected anion gap. This is especially important in hypoalbuminemia, where the https://anion-gap-guide320.lumenforgex.com/posts/anion-gap-calculator-used-for-assessing-non-anion-gap-metabolic-acidosis unadjusted value may look falsely low.
The aim of the adjustment is to adjust for low negatively charged protein levels. In other words, if albumin is reduced, the measured gap may overlook the presence of excess acids. A corrected value can therefore offer a better picture of the patient’s real acid-base status.
Various correction methods exist, and the exact approach may vary by clinician or institution. The important point is that the adjustment should be used when albumin is abnormal, because it increases the usefulness of the anion gap as a screening tool and promotes more accurate patient evaluation.
Albumin correction does not override the original result. Instead, it provides context and helps prevent missing a significant acid-base imbalance when albumin is low.
Frequent Causes of an Abnormal Anion Gap
An abnormal anion gap may indicate several different disorders, so the result must be related to the rest of the case. Frequent causes of a high value include:
- Metabolic acidosis with acid buildup Lactic acidosis Ketoacidosis Renal failure Toxin ingestion
In addition, certain substances can affect the calculation or mimic an abnormal pattern. Some toxic exposures disrupt the expected balance of measured and unmeasured ions. A careful review of medications, exposures, and symptoms is part of accurate clinical interpretation.
A low value may stem from hypoalbuminemia, lab error, or other analytical issues. Since the anion gap is derived from a blood chemistry panel, the quality of the input values directly influences the final result. That makes it a helpful but indirect marker in a broader medical assessment.
Whenever the result is abnormal, clinicians should ask whether the pattern fits the patient’s condition, whether the value is consistent with the lab’s reference range, and whether repeat testing is needed.
Interpreting Results Safely
The safest way to interpret an anion gap is to consider more than the number itself. The result is part of a wider context that includes the patient’s symptoms, other laboratory data, and the suspected cause of any acid-base balance problem. A single value does not mean a diagnosis.
First, confirm the number against the reporting lab’s normal range and reference range. Then assess whether the patient has evidence of metabolic acidosis, kidney dysfunction, infection, diabetes complications, or a possible toxin ingestion. If albumin is low, consider a corrected anion gap before drawing conclusions.
It is equally important to remember that the anion gap is a diagnostic indicator, not a total explanation. It may indicate a category of issues, but further testing may be needed to identify the exact cause. That may include repeat chemistry tests, blood gas testing, lactate measurement, ketones, kidney function studies, or toxicology evaluation.
Practically speaking, apply the anion gap as a systematic part of the medical interpretation of unexpected blood test results. Such an approach helps reduce missed abnormalities and supports better care.
Frequently Asked Questions
How is the anion gap calculated?
The conventional anion gap equation is serum sodium minus serum chloride plus serum bicarbonate. In written form, it is: Anion gap = sodium − (chloride + bicarbonate). Many anion gap calculator resources follow the exact formula.
What is a normal anion gap value?
The usual range is determined by the testing facility and its reference interval, but many values fall in the lower single digits to low teenage range when reported in mEq/L. Always compare the value with the lab’s own reference standard rather than relying on one universal cutoff.
Why might an anion gap be high?
A elevated anion gap often suggests extra acids or unmeasured anions exist. Common causes include lactic acidosis, ketoacidosis, renal failure, and certain kinds of toxin ingestion. It is often a clue to metabolic acidosis or another disorder of acid-base balance.
Is a low anion gap serious?
Yes, although it is uncommon. A reduced anion gap may stem from low albumin, testing error, or other abnormalities. It may be benign in some cases, but it can also suggest an issue that warrants further testing, especially if other blood test results are not normal.
Should albumin be used to correct the anion gap?
Absolutely, albumin should be considered when interpreting the result, especially if albumin is low. Correction for albumin can provide a more accurate anion gap after correction and help avoid missing a hidden metabolic issue. This is particularly useful in low albumin and during broader clinical assessment.